
Medigap vs Medicare Advantage
Medigap vs Medicare Advantage

Medigap versus Medicare Advantage is one of the most important choices you will make in Medicare, because it determines how you access doctors, how your bills appear throughout the year, and how much control you have over provider networks, specialist referrals, and prior authorization requirements. At Diversified Insurance Brokers, Tonia Pettitt, CMIP©, and Jason Stolz, CLTC, CRPC, DIA, CAA, break down both paths in plain language: how Medigap (Medicare Supplement) works alongside Original Medicare, how Medicare Advantage (Part C) replaces Original Medicare with a private plan, and what those differences mean for your budget, prescriptions, and lifestyle across a retirement that may span two or more decades.
There is no universal best option. The better choice is consistently the one that matches your real-world care pattern — which doctors you want to keep, how frequently you see specialists, what prescriptions you take, whether you travel or split time between states, and how you prefer to manage healthcare costs across the year. Some people prefer paying more each month to reduce point-of-service surprises and maintain the most predictable possible annual cost. Others want the lowest possible premium and are comfortable with copays and network structures. This guide helps you compare both paths, avoid timing mistakes that create permanent consequences, and use a cost calculator to model your own likely annual spend under each approach. How Medicare works provides the complete structural overview of all four parts that frames where this Medigap versus Advantage decision sits within the larger Medicare picture. Whether Medicare is expensive covers the total cost framework that helps retirees evaluate plans based on realistic annual spending rather than premium alone.
Free Medicare Comparison
We’ll verify your doctors and drugs, compare local plans, and estimate your true annual costs.
Request My ComparisonTwo Paths, Two Experiences
At a high level, Medigap and Medicare Advantage solve different problems through fundamentally different structural approaches. Medigap is designed to reduce cost-sharing exposure and preserve broad access to providers by pairing a Supplement policy with Original Medicare — Parts A and B remaining in effect as the primary coverage, with the Medigap plan covering some or all of the deductibles, copays, and coinsurance that Original Medicare leaves to the enrollee. Medicare Advantage is designed to manage care through a private plan that bundles coverage features — typically including hospital, medical, and prescription drug coverage — often adding supplemental benefits including dental and vision, and usually offering lower upfront premiums alongside a defined annual maximum out-of-pocket for in-network care.
Medigap keeps you on Original Medicare and adds a secondary policy that helps pay for deductibles, copays, and coinsurance. Because you remain on Original Medicare, you can typically visit any provider nationwide who accepts Medicare — approximately 93% of all practicing physicians — without network approval, without specialist referrals in most cases, and without prior authorization requirements for most standard Medicare-covered services. That simplicity matters if you want specialist access without managed care friction, if your care team spans multiple health systems, or if you spend extended time in another state. Most Medigap users add a separate Part D plan for prescription coverage, which allows you to shop drug coverage independently each year based on your medication list rather than being limited to whatever formulary is bundled with a medical plan. Medicare Supplement Plan G versus Plan N covers how people balance premium level against point-of-service copays across the two most commonly selected Medigap designs for new enrollees. The best Medicare Supplement plans for seniors covers carrier evaluation across the standardized Medigap plan letter designations.
Medicare Cost Calculator
Use the calculator below to get a quick, visual sense of how premiums and cost sharing stack up for your situation. We will validate everything with carrier quotes and your exact doctors and medications, but this is a fast way to orient the comparison before we build a plan-specific projection.
Medicare Advantage replaces Original Medicare with a private HMO or PPO that delivers Medicare benefits through the plan’s network and benefit structure rather than through Original Medicare’s direct fee-for-service system. Many Advantage plans bundle Part D drug coverage, and many include dental, vision, hearing, fitness, and other supplemental benefits. Premiums can be low — and in some areas $0 above the Part B premium — so Advantage can appear to be the most affordable option at first comparison. The trade-off is managed care structure: provider networks, referral requirements in HMO designs, and prior authorization processes for certain services and medications all play a larger role in how you access care than they do under Original Medicare with a Medigap supplement. For a complete structural refresher on how these two approaches compare across all major dimensions, see Medicare Supplement versus Medicare Advantage and Medicare Advantage versus Medicare Supplement comparison.
| Comparison Factor | Medigap (Medicare Supplement) | Medicare Advantage (Part C) | Best Fit |
|---|---|---|---|
| Monthly premium | Higher — Plan G averages $100–$250/mo depending on age and location; separate Part D adds $15–$60/mo | Often lower or $0 above Part B premium; drug coverage typically bundled | Advantage if minimizing monthly premium is the priority; Medigap if minimizing total annual exposure |
| Annual out-of-pocket maximum | Very low — Plan G leaves only the $257 Part B deductible (2025); no annual cost-sharing cap needed | Up to $9,350 in-network; combined in/out-of-network cap up to $14,000 (2025) | Medigap for retirees with chronic conditions, frequent specialist use, or high healthcare utilization |
| Provider access | Any Medicare-accepting provider nationwide — no network, no referrals required in most cases | Network-based; HMO requires referrals; PPO allows out-of-network at higher cost | Medigap for established specialist relationships, multi-system care, or second opinions at specialized centers |
| Travel and multi-state coverage | Routine care covered nationwide with any Medicare-accepting provider; no geographic restriction | Emergency care covered nationwide; routine care generally limited to plan’s service area | Medigap for snowbirds, retirees with second homes, or frequent travelers needing routine care access |
| Prescription drug coverage | Not included — requires standalone Part D plan; allows independent formulary selection each year | Usually bundled; formulary tied to plan and changes annually | Medigap + standalone Part D for retirees on specialty or brand-name medications needing formulary flexibility |
| Dental, vision, hearing | Not included; requires standalone dental and vision plans added separately | Often bundled; scope varies widely — verify coverage caps and network before relying on bundled benefits | Advantage if bundled benefits genuinely cover anticipated dental and vision needs; verify before enrolling |
| Prior authorization requirements | Generally not required for Medicare-approved services; Original Medicare rules govern | Common for specialist referrals, imaging, inpatient admissions, and certain medications | Medigap for retirees who want to avoid managed care administrative friction |
| Plan stability year to year | Benefits standardized by federal law; only premium changes annually; no network or benefit shifts | Networks, formularies, copays, and supplemental benefits change annually; requires annual review | Medigap for retirees who want coverage that doesn’t require annual re-evaluation to maintain value |
| Switching flexibility later | Can switch to Advantage at annual open enrollment without underwriting | Switching back to Medigap after open enrollment window typically requires medical underwriting in most states | Starting with Medigap during the guaranteed-issue window preserves long-term flexibility that Advantage enrollment does not |
Access to Doctors and Hospitals
For many retirees, provider access is the single most consequential factor in the Medigap versus Advantage decision — and the one most frequently underweighted in comparisons that focus primarily on premium. With Medigap, the rules are typically straightforward: if a doctor, specialist, or hospital accepts Medicare assignment, you can generally access that provider without network approval, without a primary care physician referral, and without prior authorization for most standard Medicare-covered services. That freedom matters if you want to see a specialist at a different health system than your primary care physician uses, if you want to seek a second opinion at a specialized treatment center, or if you want to maintain established relationships with multiple specialists managing different chronic conditions simultaneously. For retirees who travel frequently or who split time between two states, Medigap’s portability eliminates the access friction that network-based coverage creates when routine care is needed outside the plan’s defined service area.
With Medicare Advantage, the provider network is a real-world planning factor that must be verified before enrollment — not after. Emergency and urgently needed care are covered nationwide as a federal requirement, but routine non-emergency care is generally designed around the plan’s defined service area and in-network provider panel. PPO plans allow out-of-network access at higher cost-sharing levels, but the specific out-of-network rules, cost-sharing percentages, and whether out-of-network costs count toward the annual out-of-pocket maximum vary by carrier and plan design. Advantage can be an excellent value when the local network is strong, your specific physicians participate, and your care needs are primarily managed within a single health system — but it can create real access and financial complications when preferred specialists or hospital systems are outside the network. Medicare for people with chronic conditions addresses how ongoing specialist care needs and multi-provider care coordination specifically affect the provider access consideration in this decision. Medicare Supplement coverage for cancer treatment illustrates why unrestricted provider access matters most in high-stakes medical situations where specialist choice and treatment center access can directly affect outcomes.
One of the most common and costly mistakes in Medicare plan selection is choosing a plan based on premium before verifying provider participation. A plan that saves on monthly premium can produce higher total annual costs through out-of-network charges, lost specialist relationships, or the disruption costs of switching providers mid-treatment. Our process at Diversified Insurance Brokers begins with providers and prescriptions — then we look at cost structure.
Drugs, Dental, Vision, and the Extras
Prescription coverage and supplemental benefits are where Medicare Advantage often looks most attractive in initial comparison, and where the most important verification work is required before drawing conclusions. Many Advantage plans include Part D prescription drug coverage as a bundled component, so drug benefits are included without a separate plan or premium. They may also include dental, vision, hearing, and wellness program benefits that Original Medicare and Medigap do not cover. If dental and vision needs are anticipated, the bundled approach can be valuable — but verifying that the bundle actually meets specific needs is essential, because dental networks, annual benefit caps, covered service categories, and plan rules vary widely across plans that all market themselves as including dental coverage. A plan that covers two preventive dental cleanings annually is categorically different from a plan that covers major restorative work with a meaningful annual maximum, even though both are described as “including dental.”
Medigap does not include prescription drug coverage or supplemental benefits. The standard Medigap strategy combines Original Medicare, a Medigap plan for medical cost-sharing, and a standalone Part D plan for prescriptions. Some people prefer this three-part structure because it allows independent optimization of each component — choosing the Part D plan whose formulary best covers current medications at the most favorable tier placement, without being constrained to the bundled drug formulary of a Medicare Advantage plan. Others prefer the simplicity of one bundled plan. Either way, the annual drug cost analysis comes down to the specific medication list, preferred pharmacies, formulary tier placement, and whether prior authorization or step therapy requirements apply to key medications. Medicare plans with dental and vision coverage covers how dental and vision benefits are structured across both Advantage bundled plans and standalone supplemental options. The Medicare Part D donut hole covers how drug cost phases work and how the 2025 $2,000 out-of-pocket cap changed the financial picture for higher-cost drug users under both Advantage and standalone Part D structures.
Costs: Premiums vs. Total Annual Exposure
Most people begin the Medicare comparison by asking which option is cheaper. The more precise and more useful question is which option is cheaper over a full year given realistic healthcare utilization — because the answer to that question is frequently different from the answer to the simpler premium comparison question. Medigap premiums are consistently higher than most Medicare Advantage premiums, but the point-of-service costs under Medigap are typically lower and substantially more predictable. A Plan G enrollee pays a higher monthly premium but faces minimal cost-sharing for Medicare-approved services beyond the annual Part B deductible — which in 2025 is $257. For retirees with moderate to high healthcare utilization — regular specialist visits, diagnostic imaging, outpatient procedures, or chronic condition management — Medigap’s higher-premium, lower-cost-sharing structure often produces a lower total annual cost than Advantage, and almost always produces more predictable annual budgeting.
Medicare Advantage frequently inverts this equation. Monthly premiums may be low, but copays and coinsurance accumulate across the year as services are used — a $45 specialist copay, a $300 per-day hospital copay for the first several days of an inpatient stay, a 20% coinsurance on outpatient surgery, and so on until the plan’s annual out-of-pocket maximum is reached. In 2025, Medicare Advantage in-network out-of-pocket maximums are capped federally at $9,350, and combined in-network and out-of-network maximums can reach $14,000. In a healthy low-utilization year, the Advantage premium savings can be substantial. In a year with significant healthcare events — a hospitalization, a surgery, intensive outpatient therapy, or an extended specialist workup — total annual cost under Advantage can approach or reach the maximum out-of-pocket, which may exceed what Medigap would have cost all year including premium. Low-cost Medicare plans for retirees covers the total annual cost comparison framework that produces genuinely low-cost outcomes rather than low-premium outcomes that may carry high utilization costs. Medicare quotes and plan options covers the quoting and comparison process that makes these annual cost projections concrete and plan-specific rather than theoretical.
Travel and Second Homes
If you spend extended stretches outside your home state — whether as a snowbird, a frequent traveler, or a retiree with a second home — Medigap’s nationwide provider access can be a decisive practical advantage. Under Original Medicare with a Medigap supplement, you can generally schedule routine appointments, specialist consultations, and follow-up care with any Medicare-accepting provider anywhere in the country — not just emergencies. Medicare Advantage plans cover emergency and urgently needed care nationwide as a federal requirement, but routine non-emergency care outside the plan’s defined service area is typically not covered at in-network rates and may not be covered at all for HMO designs. PPO Advantage plans can soften this limitation, but out-of-network cost-sharing can be substantial and must be specifically verified for the geographic areas where you regularly spend time.
Prescription access while traveling also requires planning. If you fill prescriptions at pharmacies in multiple states, confirming that the plan’s preferred pharmacy network includes accessible locations in all areas where you regularly spend time can prevent paying non-preferred pharmacy pricing for medications throughout part of the year. Mail-order pharmacy benefits, when available, can reduce this friction for maintenance medications. These details may seem minor individually but can produce meaningful annual cost differences for retirees who genuinely split their year between geographic locations.
Enrollment Timing and Switching Rules
Enrollment timing is the hidden variable in the Medigap versus Advantage decision — one that creates lasting consequences that many retirees do not discover until they want to change their coverage structure and find that their options are more constrained than anticipated. The Initial Enrollment Period around age 65, and especially the Medigap Open Enrollment window — the six months beginning when Part B starts — represent the most flexible and most protected entry point for Medigap coverage. During that window, insurers are required to accept all Medigap applicants without medical underwriting in most states, meaning carriers cannot decline coverage or charge higher premiums based on health history regardless of pre-existing conditions. After that window closes, Medigap applications in most states are subject to full medical underwriting — carriers can decline coverage, charge substantially higher premiums, or exclude pre-existing conditions based on health history.
This asymmetry creates a critical planning consideration: switching from Medicare Advantage back to Medigap later in life — when health conditions may have developed — can be significantly more difficult and expensive than starting with Medigap during the guaranteed-issue open enrollment window. Medicare Advantage plan changes are made annually during the Annual Enrollment Period (October 15 through December 7) and can be adjusted without medical underwriting, but switching into Medigap from Advantage outside of specific guaranteed-issue situations typically requires underwriting. A retiree who starts with Advantage at 65 and wants to switch to Medigap at 70 after developing a chronic condition may find that Medigap coverage at preferred rates is no longer accessible. Medicare Part B penalties and SEPs covers the enrollment timing rules and Special Enrollment Period mechanics. What to know before you enroll in Medicare covers the complete pre-enrollment preparation framework. Medicare enrollment mistakes to avoid covers the specific errors that create permanent coverage and cost consequences. How to switch Medicare plans covers the annual review and switching process for enrollees whose current coverage no longer fits their situation.
How to Decide: A Practical Framework
A practical decision framework begins with three lists: your current doctors and hospitals and whether they accept Medicare assignment, your prescriptions and preferred pharmacies and what each plan’s formulary covers at which tier, and your travel or multi-state living patterns and how often you need routine care outside a single geographic area. If provider access and portability are non-negotiable priorities, Medigap is typically the safer structural choice because it preserves access regardless of network without requiring annual verification that specific providers still participate. If your physicians and specialists are all comfortably inside a strong local network and you value bundled supplemental benefits and lower monthly premiums, a Medicare Advantage PPO may offer excellent total value in typical utilization years.
Budget style is the second dimension. If your priority is fewer surprise bills and the most predictable possible annual cost structure regardless of healthcare utilization, Medigap’s higher-premium, lower-cost-sharing design consistently produces that outcome. If your priority is the lowest possible monthly premium and you are comfortable absorbing per-service copays and coinsurance as you use care — knowing that a bad health year could push you toward the plan’s annual out-of-pocket maximum — Advantage may fit that preference. Neither is wrong as a preference; they simply point toward different plan designs. The most accurate answer for any individual is always a side-by-side total annual cost projection based on actual providers, actual medications, and realistic utilization expectations. What IRMAA is covers the income-related premium surcharges that affect both Part B and Part D costs under either plan structure. The best independent Medicare broker covers why working with an independent advisor who has access to the full carrier market — rather than a captive agent or single-carrier representative — produces the most competitive and most complete Medicare plan selection. Getting a second opinion on your Medicare quote is the most direct path to confirming that the coverage option presented to you represents the best available in the full market. The Medicare playbook provides the comprehensive strategic framework for making all Medicare decisions — Parts A, B, C, and D, Medigap, IRMAA, enrollment timing, and annual review — in an integrated way.
Have Us Check Your Doctors and Drugs
Send your list and we’ll build a side-by-side comparison with true annual costs for each path.
Request a ComparisonPrefer to talk? 📞 800-533-5969
Why Work With Diversified Insurance Brokers
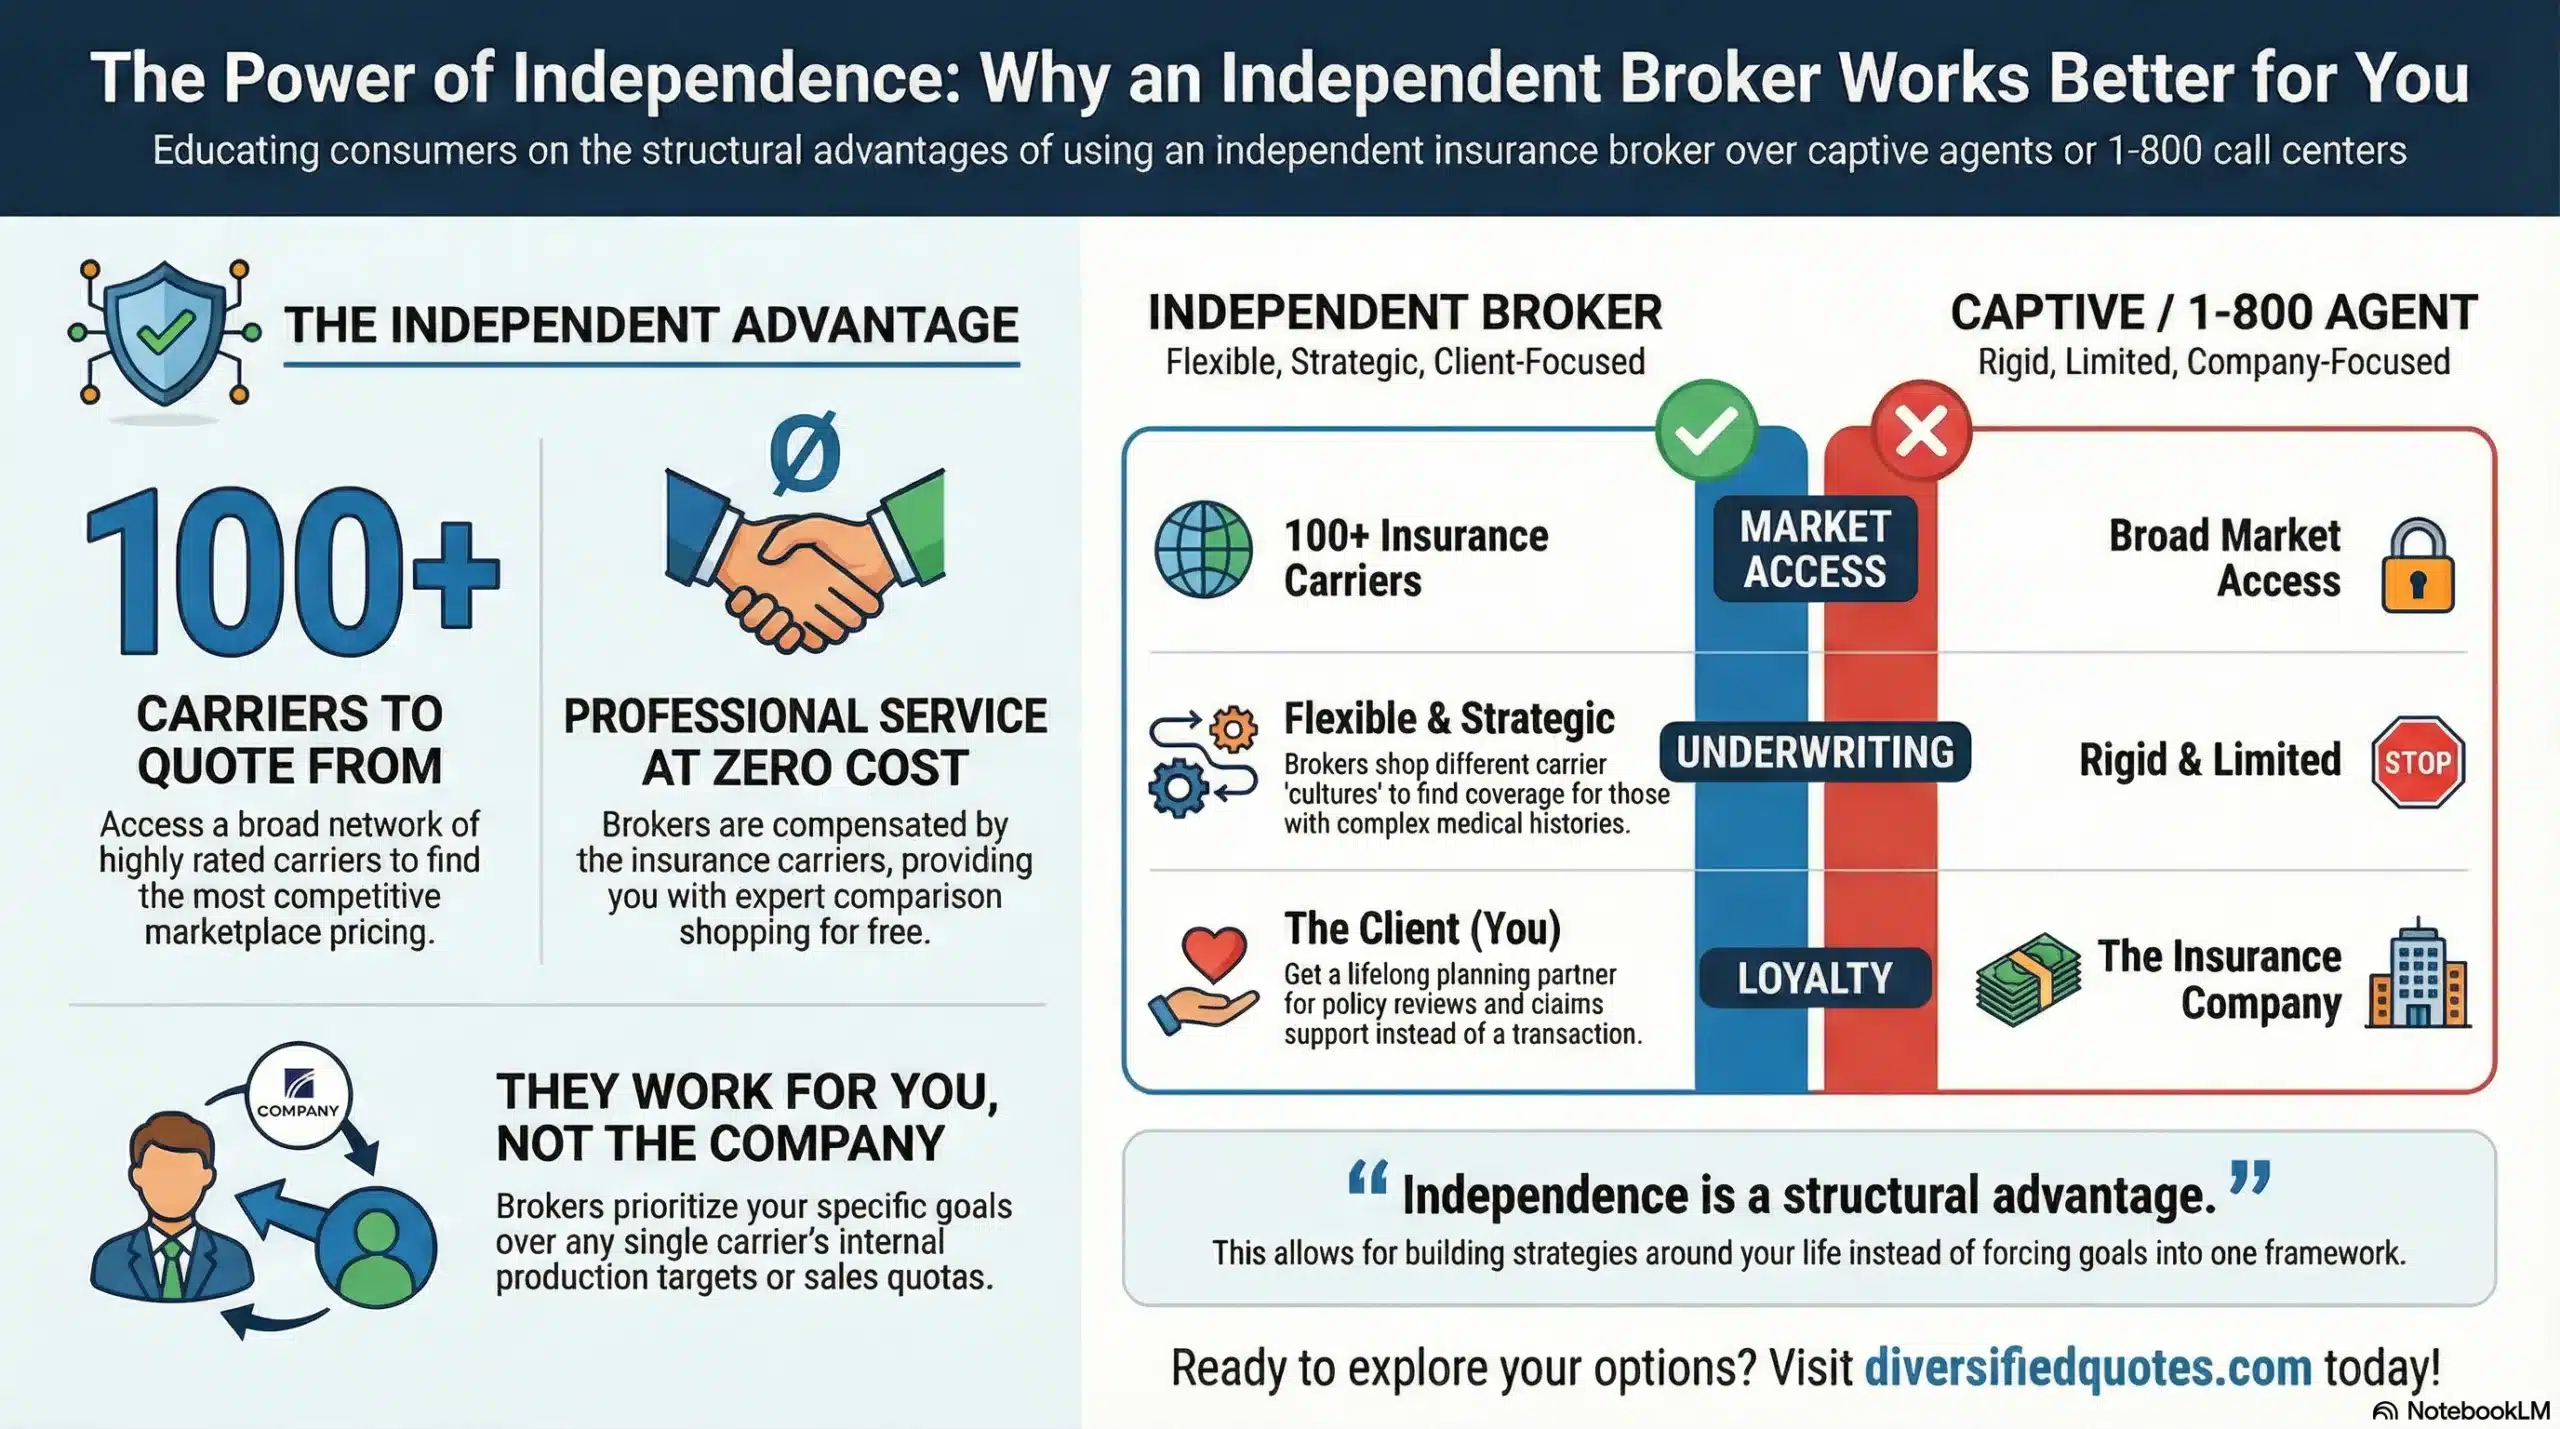
Since 1980, Diversified Insurance Brokers has helped clients compare the two Medicare paths without sales pressure from any single carrier. We verify provider networks and drug formularies, model total annual spend under each plan structure based on actual utilization inputs, and flag plan rules — prior authorization requirements, network limitations, formulary restrictions — that can affect real-life access to care in ways that premium comparisons miss entirely. Because we work independently across more than 100 carriers, our recommendations begin with your doctors, prescriptions, budget style, and geographic lifestyle — not a single company’s available plan menu. After enrollment, we remain available for annual reviews and plan adjustments so your coverage keeps pace with changes in your health, your providers, and the plans themselves. Medicare enrollment for people still working covers the coordination framework for active employees approaching Medicare eligibility who need to understand when delaying coverage is safe and when it creates penalty risk. How Medicare and Social Security work together covers the financial integration that affects monthly net income in retirement. The pre-retirement checklist provides the sequencing framework for aligning all Medicare decisions with Social Security, income planning, and tax strategy before retirement begins.
Related Topics to Explore
Continue your Medicare research with these related guides.
Compare Medicare Carriers
Book a free consultation with Tonia to review highly-rated Medicare Advantage plans and choose the best fit for your retirement.
Frequently Asked Questions: Medigap vs Medicare Advantage
What is the main difference between Medigap and Medicare Advantage?
Medigap works alongside Original Medicare — you keep Parts A and B as your primary coverage and the Medigap plan pays some or all of the cost-sharing Medicare leaves to the enrollee, with access to any Medicare-accepting provider nationwide without network restrictions. Medicare Advantage replaces Original Medicare with a private plan that bundles hospital, medical, and usually prescription drug coverage, often adding dental and vision benefits, using provider networks with per-service copays and an annual out-of-pocket maximum. The structural choice is essentially when you prefer to pay: consistently each month in premium under Medigap, or as you use services throughout the year under Advantage until reaching the annual maximum.
Can I switch from Medicare Advantage to Medigap later?
You can switch from Medicare Advantage to Medigap at the annual open enrollment period, but in most states the Medigap application will be subject to full medical underwriting after the initial six-month Medigap open enrollment window that begins when you turn 65 and enroll in Part B. Carriers can decline coverage or charge higher premiums based on health conditions developed since original enrollment. This asymmetry is one of the most important planning considerations in the initial Medicare decision — starting with Medigap during the guaranteed-issue open enrollment window preserves long-term flexibility in ways that starting with Advantage does not, because Advantage enrollees who later want Medigap may find it unavailable or unaffordable if health has changed.
Which is better for people who travel or live in multiple states?
Medigap is generally better for travelers and retirees who split time between states. Medigap works with any Medicare-accepting provider anywhere in the country without network restrictions, so routine care, specialist visits, and follow-up appointments can be scheduled wherever you are. Medicare Advantage covers emergency and urgently needed care nationwide as a federal requirement, but routine non-emergency care is typically covered only within the plan’s defined service area. A retiree spending several months in a different state on a home-state Advantage plan generally cannot schedule routine appointments at in-network rates in that second location. For multi-state retirees, this geographic limitation frequently drives the decision toward Medigap.
Does Medicare Advantage include prescription drug coverage?
Most Medicare Advantage plans include prescription drug coverage as a bundled component, but not all. When drug coverage is bundled, the formulary is specific to that plan and changes annually — a medication covered at a favorable tier in year one may move to a higher tier or be removed from the formulary in year two. Medigap plans do not include drug coverage, requiring a separate standalone Part D plan. While this adds administrative complexity, it also allows independent selection of the Part D plan whose formulary best covers specific medications at the most favorable tier placement, without being constrained to whatever formulary is bundled with the medical plan. For retirees on brand-name or specialty medications, this formulary independence can produce significantly lower annual drug costs.
Which is cheaper — Medigap or Medicare Advantage?
The answer depends on total annual cost including all premiums, copays, coinsurance, and drug costs — not just monthly premium. Medigap premiums are consistently higher than most Medicare Advantage premiums, but the point-of-service costs under Medigap are typically much lower and more predictable, with Plan G enrollees facing minimal cost-sharing beyond the annual Part B deductible of $257 in 2025. Medicare Advantage may have lower or $0 premiums but accumulates copays and coinsurance throughout the year, with in-network out-of-pocket maximums capped at $9,350 in 2025. For retirees with moderate to high healthcare utilization, Medigap’s total annual cost often compares favorably despite its higher premium. The only reliable way to answer the “which is cheaper” question for a specific individual is a side-by-side projection based on actual providers, actual medications, and realistic utilization patterns.
About the Author:
Tonia Pettitt, CMIP©, (NPN 14374308), is a seasoned Medicare specialist with more than 40 years of hands-on experience guiding individuals and families through the complexities of Medicare planning. As a senior advisor with the nationally licensed independent agency Diversified Insurance Brokers, Tonia provides clear, dependable guidance across all areas of Medicare—including Medicare Advantage, Medicare Supplement (Medigap), and Part D prescription coverage. Leveraging active contracts with dozens of highly rated insurance carriers, she helps clients compare options objectively and secure the most suitable coverage for their health and budget.
Known for her patient, education-first approach, Tonia has built a reputation as a trusted resource for retirees seeking reliable, unbiased Medicare support. With four decades of experience across evolving Medicare laws, carrier changes, and plan structures, she brings unmatched insight to every client conversation—ensuring clients feel confident, protected, and fully prepared for each stage of their retirement healthcare journey.
Explore More Medicare Options: Browse our complete guide to Medicare Advantage vs Medicare Supplement — covering plan comparisons, supplement plans, Advantage plans & finding the best coverage.
Last Reviewed: June 15, 2026 |
Reviewed by: Tonia Pettitt, CMIP©
Medicare Specialist, Diversified Insurance Brokers, Inc. | NPN: 14374308 | Diversified Insurance Brokers, Inc. — Licensed in all 50 states
Fact Checked by: Jason Stolz, CLTC, CRPC, DIA, CAA
Chief Underwriter, Diversified Insurance Brokers, Inc. | NPN: 20471358 | Diversified Insurance Brokers, Inc. — Licensed in all 50 states
Did you find this content helpful? Leave us a Google review — it helps others find trustworthy guidance too.
Editorial Standards: Diversified Insurance Brokers maintains rigorous editorial standards to ensure accuracy, clarity, and independence in all content. Learn more about our editorial standards and commitment to transparency.
