
Life Insurance with STDs
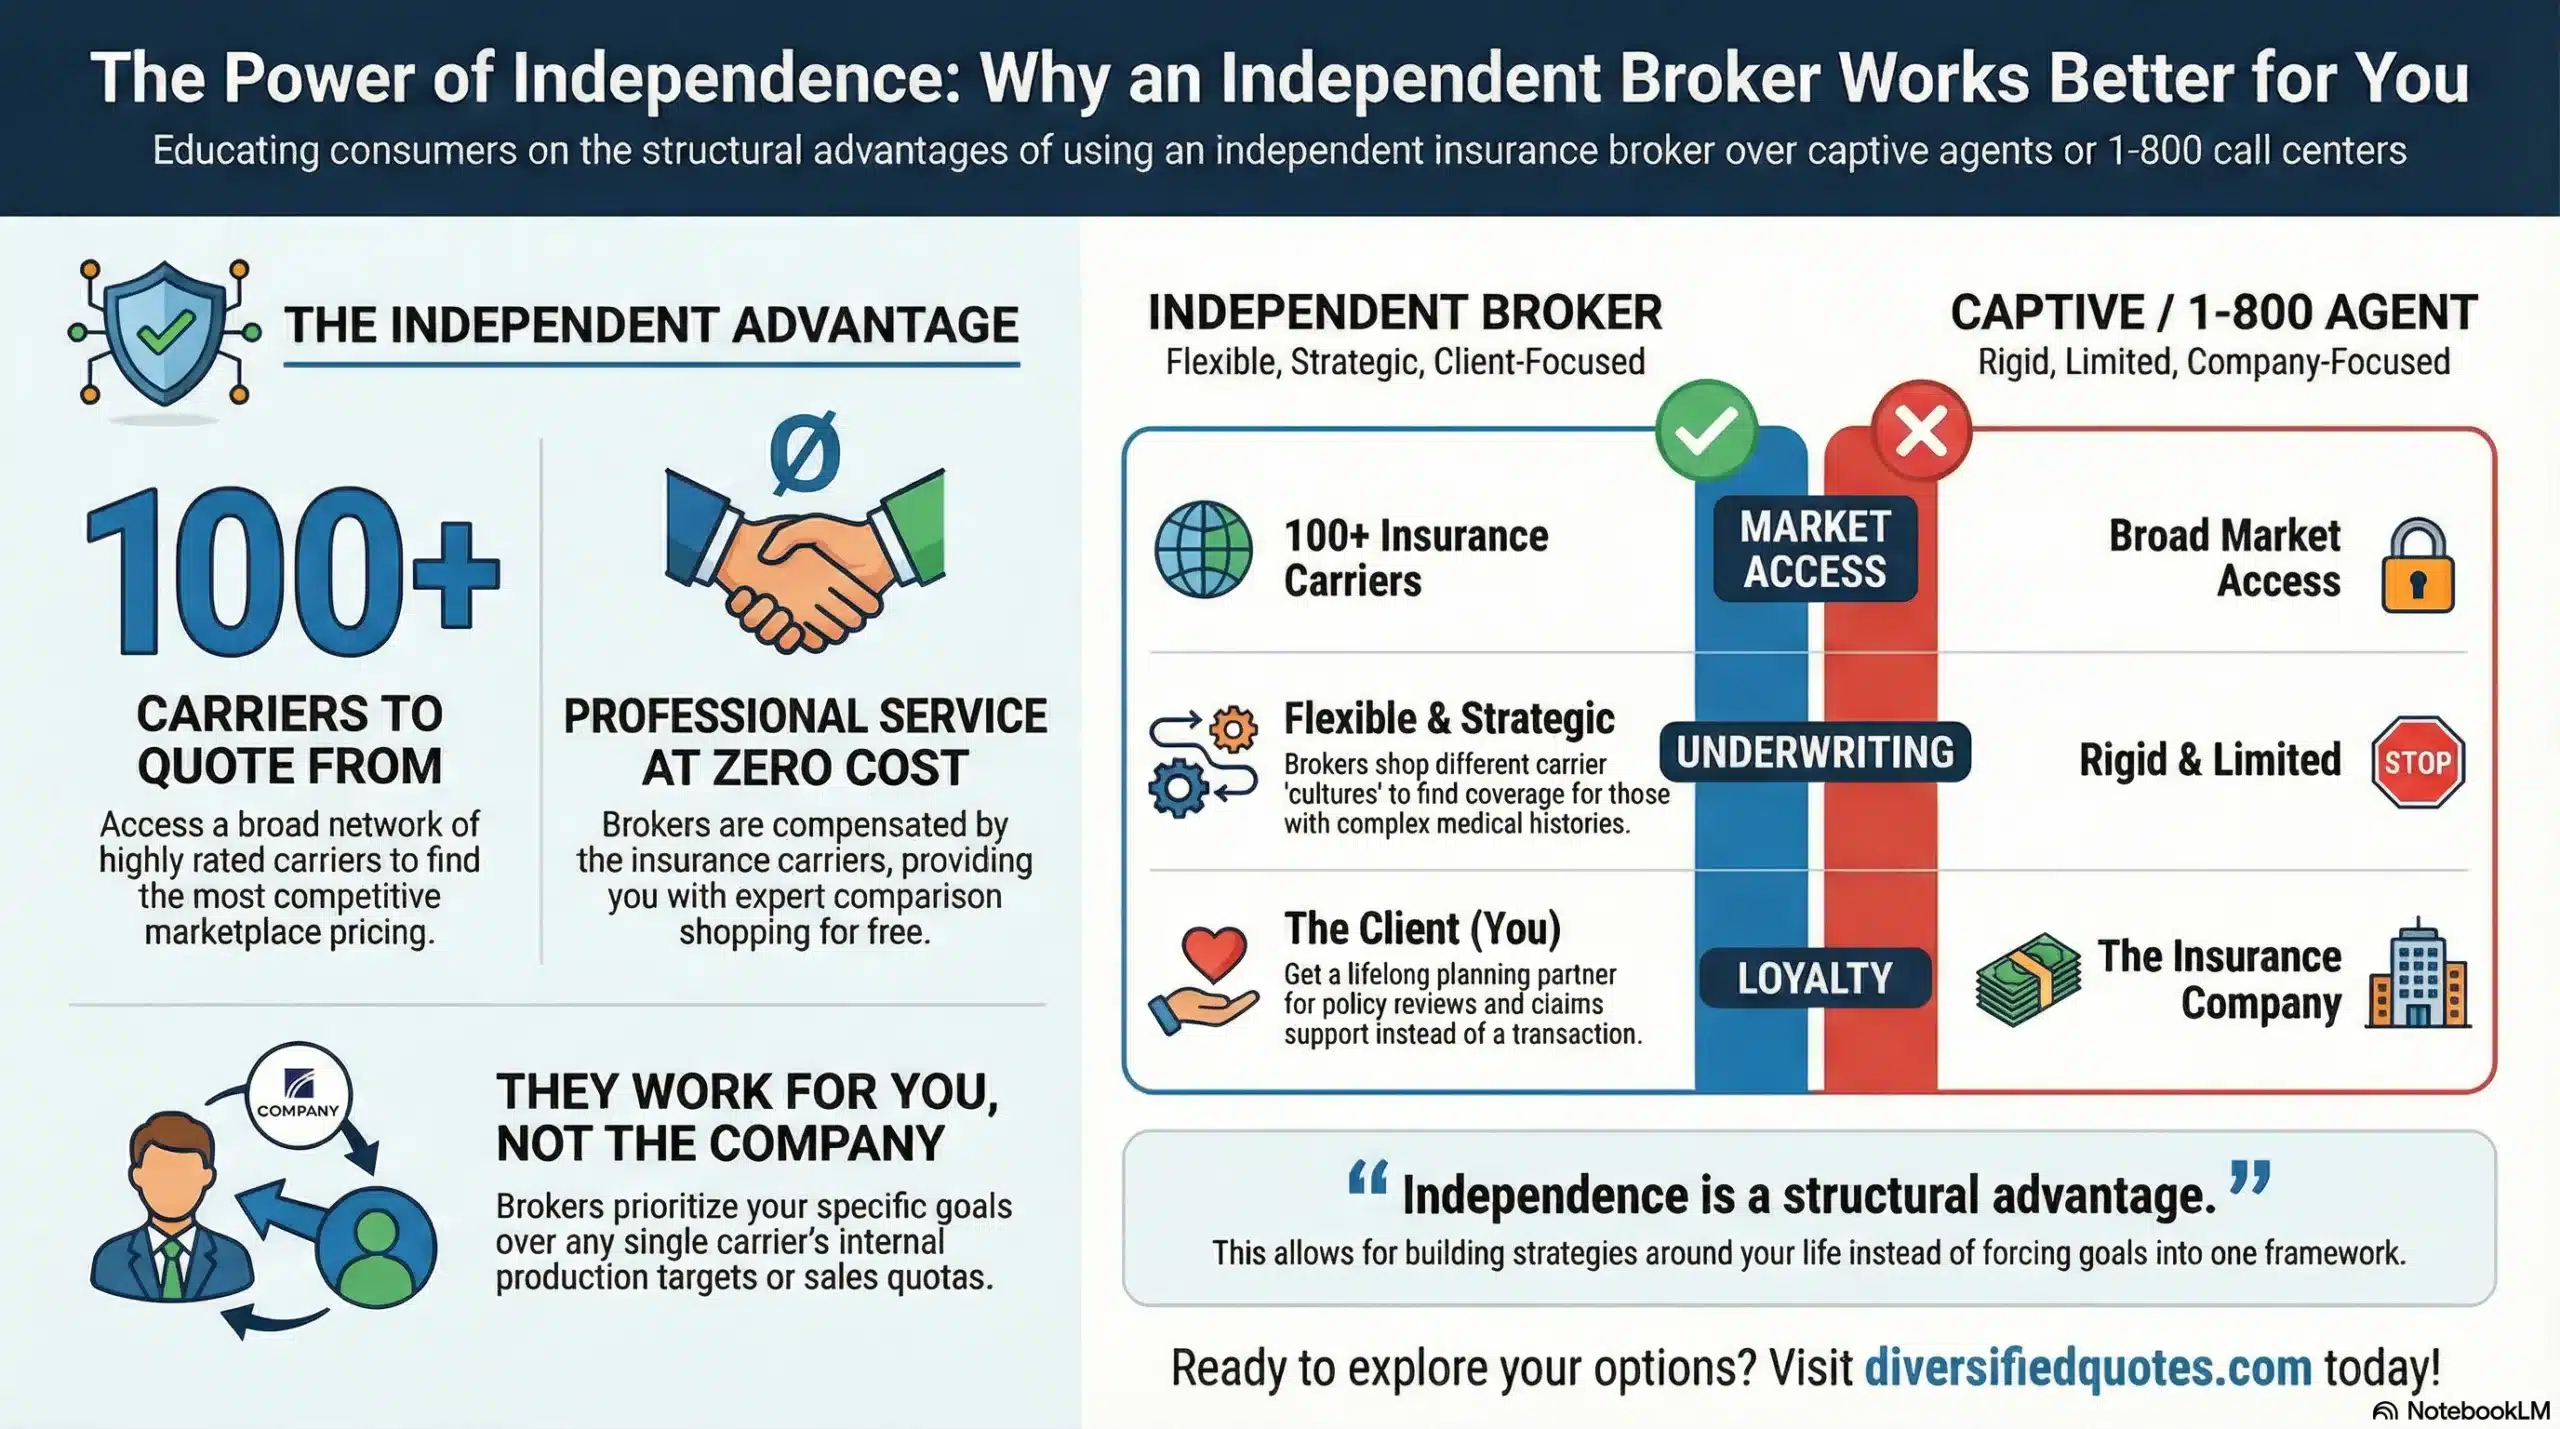
As an Independent Life Insurance Broker, we compare rates across 100+ carriers and prescreen every application before submission.
Life Insurance with STDs

Jason Stolz CLTC, CRPC, DIA, CAA
Most people who call us with a question about a past or current sexually transmitted disease are bracing for bad news that, in the large majority of cases, simply isn’t coming. Sexually transmitted infections cover an enormous range of conditions, from ones that clear on their own without any lasting health impact, to ones that are now curable in a matter of weeks with modern treatment, to a small handful that genuinely do require careful underwriting attention. Treating all of them as one undifferentiated, disqualifying category is the single biggest misconception we encounter on this topic, and it’s simply not how underwriting actually works.
Jason Stolz, CLTC, CRPC, DIA, CAA, is Chief Underwriter at Diversified Insurance Brokers and has placed coverage across the full range of STD-related histories long enough to know exactly which specific facts move a case toward standard rates and which don’t matter at all. As an independent broker working across dozens of carriers, our office can tell you plainly, and confidentially, what a specific diagnosis actually means for your application, rather than leaving you to guess based on stigma or outdated assumptions. If you’re specifically researching coverage with an HIV diagnosis, we’ve built a dedicated page on life insurance with HIV or AIDS, since that condition follows its own distinct underwriting path; this page covers the full range of other sexually transmitted diseases and infections.
Navigating life insurance with an STD history and want a confidential, honest answer? Let’s talk.
Talk to a Life Insurance Specialist
| Condition | General Underwriting Reality | What Actually Matters |
|---|---|---|
| Genital herpes (HSV-1 or HSV-2) | Essentially a non-issue for most applicants — doesn’t affect life expectancy | Nothing further in most cases; rarely even a follow-up question |
| HPV (human papillomavirus) | The virus itself is not evaluated — extremely common and usually clears on its own | Only a related finding (abnormal Pap smear, dysplasia, or cancer) is relevant, not the HPV label |
| Chlamydia or gonorrhea, treated | Generally a non-issue once treatment is confirmed complete | Confirmation of completed antibiotic treatment and resolution |
| Syphilis, treated in early stages | Generally favorable — early treatment is curative with no lasting impact | Confirmed treatment and no evidence of cardiovascular or neurological involvement |
| Syphilis, untreated for years or diagnosed late | A genuinely different, more complex case | Full neurological and cardiovascular workup to rule out late-stage complications |
| Hepatitis B or C, cured or well-controlled | Often standard or near-standard rates achievable, with the right documentation | Confirmed viral suppression or cure, liver function results, and a waiting period since treatment |
| Hepatitis B or C with cirrhosis or ongoing active infection | A more complex file requiring individual assessment | Current liver function, specialist follow-up, and staging of any liver damage |
Outcomes above reflect general, well-documented underwriting patterns and are not a quote or a guarantee; actual results depend on the complete file and the specific carrier.
See Real-Term Rates Side by Side
Life Insurance Quoter
The Core Principle Behind Every Condition on This Page
Underwriters are not evaluating a diagnosis label. They’re evaluating a specific set of clinical facts: whether an infection is active or resolved, whether treatment was completed and confirmed effective, whether any organ damage occurred before that treatment happened, and whether ongoing monitoring shows continued stability. Two applicants can carry the identical diagnosis on paper and represent genuinely different levels of risk, depending entirely on these specifics. This is precisely why “I have herpes” and “I have hepatitis C” produce such wildly different underwriting conversations, even though both fall under the same broad umbrella term — the conditions themselves have almost nothing in common medically, and treating them as a single category obscures far more than it explains.
Herpes (HSV-1 and HSV-2): Why This One Rarely Matters at All
Genital herpes, caused by either herpes simplex virus type 1 or type 2, is extremely common and, for the overwhelming majority of people who carry it, has no effect on life expectancy whatsoever. It doesn’t damage organs, doesn’t progress to a more serious disease, and doesn’t require ongoing monitoring the way many other chronic conditions do. For life insurance underwriting purposes, a herpes diagnosis on its own is typically treated as a non-issue, and many applicants find it doesn’t come up as a meaningful factor in their application at all. This is worth knowing clearly, because the stigma attached to this particular diagnosis is often wildly out of proportion to its actual medical or financial relevance.
HPV: The Virus Isn’t the Question — The Follow-Up Finding Is
Human papillomavirus is the most common sexually transmitted infection there is, and the large majority of people who are sexually active will encounter some strain of it at some point. Most infections clear on their own, without treatment, within one to two years, and leave no lasting trace. This is why underwriters generally don’t ask about HPV as a bare diagnosis at all — the virus itself isn’t a medically actionable fact in the way a diagnosis of diabetes or heart disease would be.
What does matter is a downstream finding tied to a persistent, high-risk strain: an abnormal Pap smear, a diagnosis of cervical dysplasia, or, in less common cases, an HPV-related cancer. These are evaluated the same way any other abnormal finding or cancer history would be evaluated, based on severity, treatment, and follow-up, entirely independent of the fact that HPV was the underlying cause. If you’ve had an abnormal Pap smear or a related procedure, that’s the piece of your history worth discussing directly — not the HPV diagnosis itself.
Chlamydia and Gonorrhea: Bacterial, Treatable, Generally Resolved
Both of these are bacterial infections that respond reliably to a standard course of antibiotics, and once treatment is completed and the infection has resolved, they generally have no bearing on life insurance underwriting at all. The complication worth knowing about is pelvic inflammatory disease, which can develop if either infection goes untreated for an extended period and, in some cases, can affect fertility — but PID itself is not typically a life-expectancy-relevant condition in the way underwriters evaluate mortality risk, and a treated, resolved case of either infection is rarely a meaningful factor in an application.
Syphilis: A Condition Where Timing of Treatment Changes Everything
Syphilis progresses through recognized stages if left untreated — primary, secondary, latent, and, only after years or decades without treatment, tertiary. This staging matters enormously for underwriting, because it maps almost directly onto the actual health consequences involved. Treated with standard antibiotic therapy during the primary, secondary, or early latent stage, syphilis is curable with no lasting health impact, and a documented, completed treatment course from this stage is generally viewed favorably, similar to how a treated bacterial infection of any kind would be evaluated.
Tertiary syphilis is a genuinely different situation. Reached only after the infection has gone untreated for years, it can cause serious, sometimes irreversible damage to the cardiovascular and nervous systems, including neurosyphilis and cardiovascular syphilis. A case involving a syphilis diagnosis from many years or decades in the past, particularly one where treatment history is unclear or was delayed, generally warrants a more thorough neurological and cardiovascular workup before underwriting can proceed with confidence. The distinguishing question an underwriter is actually asking isn’t “did this person have syphilis” — it’s “was this treated before it had the chance to cause lasting damage.”
Have documentation of treatment for any of these conditions and want to know what it means for your application? Let’s look at the actual records.
Get a Confidential Case Review
Hepatitis C: How Much This Has Actually Changed
If there’s one condition on this page where the underwriting reality has shifted dramatically in a relatively short window of time, it’s hepatitis C. Older treatment regimens based on interferon, sometimes combined with ribavirin, achieved cure rates ranging from under 10% with interferon alone up to roughly 30% to 50% with the combination — a genuinely difficult, often poorly tolerated treatment with a real chance it wouldn’t work. Modern direct-acting antiviral treatment, now the standard of care, achieves sustained virologic response, the clinical definition of a cure, in the range of 93% to 98% of cases, typically over a course of just several weeks, with far better tolerability than older regimens ever offered.
Sustained virologic response means an undetectable viral load maintained for at least 12 weeks after treatment ends, and it is functionally equivalent to being cured. This is the single most important fact for anyone with a hepatitis C history to understand and document clearly, because achieving SVR is the single biggest factor separating a strong file from a difficult one.
Here’s the nuance worth understanding honestly, though: SVR is the biggest lever, but it isn’t the only one. Research following patients after achieving cure has found that most of the elevated mortality risk that remains afterward is concentrated in people who already had advanced liver damage, particularly cirrhosis, before the cure was achieved — not in people who were cured earlier in the disease’s course. In practical terms, this means two people who both achieved SVR can represent genuinely different long-term risk profiles depending on how much liver damage had already occurred by the time treatment worked. This is exactly why liver function results and any fibrosis or cirrhosis staging from before and after treatment matter as much as confirmation of the cure itself.
Many carriers require a waiting period, commonly cited in the range of one to two years after completing treatment, before offering the most favorable rate classes, and applying too early, before that window has passed, can mean landing in a less favorable rate class than the same case would receive later. Standard or near-standard rates are genuinely achievable for a well-documented, cured case; preferred rates remain less common even after a confirmed cure, which is worth knowing so expectations are realistic going in.
Hepatitis B: A Different Virus, a Different Set of Questions
Hepatitis B and Hepatitis A follows a meaningfully different path than hepatitis C. Many adults who contract hepatitis B clear the infection entirely on their own, and a documented, fully resolved acute infection is generally a minor factor in an application. A smaller share of cases become chronic, meaning the virus persists long-term, and chronic hepatitis B is managed with antiviral medication aimed at suppressing the virus to an undetectable or very low level, monitored through regular blood testing rather than cured outright the way hepatitis C now can be.
For a chronic case, what an underwriter is looking for is essentially the same pattern that matters throughout this page: confirmed viral suppression on current antiviral therapy, stable and current liver function testing, and no evidence of the cirrhosis or liver cancer risk that untreated or poorly controlled chronic hepatitis B can eventually cause. A well-managed, well-documented chronic case with years of stable suppression is a fundamentally different file than a recently diagnosed case with an incomplete workup, even though both carry the identical diagnosis label.
Building the Strongest Possible File
Across every condition on this page, the same categories of documentation make the difference between an underwriter guessing and an underwriter knowing. For any bacterial infection, confirmation that treatment was completed and the infection resolved. For hepatitis B or C specifically, viral load or SVR test results, liver enzyme panels, and, where relevant, any fibrosis or cirrhosis staging from imaging or biopsy. For a syphilis history beyond the earliest stages, documentation of the specific stage at diagnosis and confirmation of appropriate treatment. For an HPV-related history, records of the specific abnormal finding and its resolution, rather than the HPV diagnosis alone. In every case, a treating physician’s or specialist’s follow-up note confirming current stability rounds out a file that gives an underwriter genuine confidence rather than asking them to fill gaps with assumptions.
Realistic Rate Class Expectations
For herpes, treated and resolved chlamydia or gonorrhea, an HPV history with no abnormal findings, or early-treated syphilis, standard rates, and in many cases even preferred rates, are genuinely realistic outcomes, since these conditions generally carry no meaningful bearing on life expectancy once resolved. For hepatitis C with confirmed SVR and minimal pre-treatment liver damage, or hepatitis B with confirmed long-term viral suppression, standard or near-standard rates are a realistic outcome at many carriers, though a table rating is possible depending on liver function results and how much time has passed since treatment. Late-stage syphilis, active untreated infections of any kind, or hepatitis with cirrhosis already present are the cases most likely to require a longer wait, additional records, or individual assessment — and it’s worth remembering that a request for more information is not the same as a decline. Our broader overview of how rate classes work and what actually drives your premium cover this system in more depth.
Coverage Available While You Build That History
If you’re newly diagnosed, still completing treatment, or simply haven’t gathered your full documentation yet, you don’t need to go without protection in the meantime. Simplified underwriting and guaranteed issue coverage remain available immediately regardless of where your case currently stands, and many clients use exactly this kind of coverage as a bridge while a fully underwritten application is pursued once the relevant waiting period or documentation is in place.
A Note on Privacy
We recognize that this is a category of health history many people are understandably private about, and that concern is legitimate. Medical information shared as part of an insurance application is handled under standard confidentiality protections, and our office treats every conversation about a case like this the same way we’d treat any other medical history — as a factual underwriting question to be answered accurately and thoroughly, not a judgment to be made.
If You’ve Already Been Rated or Declined Elsewhere
Carriers vary meaningfully in how current their underwriting guidelines are, particularly for hepatitis C, where the shift to modern antiviral treatment has genuinely changed what a well-documented case looks like. A decline or unfavorable rating from one company is genuinely not the final word. Our second-opinion review exists specifically for cases like this, where the right documentation presented to a carrier with a more current view of the condition can produce a materially different outcome than the first quote suggested.
How We Help
We know how to read a case like this the way an underwriter does — which specific lab result or treatment record actually changes the outcome, which conditions on this page are genuine non-issues regardless of the label attached to them, and which carriers are working from current, accurate guidelines rather than outdated assumptions. Before you apply anywhere, we’ll help you gather exactly the documentation that makes your specific case strongest and match you with carriers positioned to evaluate it fairly and confidentially.
Our guidance on choosing the right policy and how much coverage you need applies the same principle we bring to every case: a diagnosis is one input among several, never the final word on what’s available to you. If you’d like to understand why working with an independent broker matters for a case like this specifically, that’s worth a direct, confidential conversation.
Ready to find out what your specific situation would actually look like to an underwriter?
Get Your Life Insurance Review
Financial Protection Essentials
Explore policy types, retirement distribution strategies, and beneficiary planning.
Talk With an Advisor Today
Choose how you’d like to connect—call or message us, then book a time that works for you.
Schedule here:
calendly.com/jason-dibcompanies/diversified-quotes
Licensed in all 50 states • Fiduciary, family-owned since 1980
Does having herpes affect my ability to get life insurance?
In almost all cases, no. Genital herpes doesn’t affect life expectancy, doesn’t cause organ damage, and doesn’t require the kind of ongoing monitoring that many other chronic conditions do. Underwriters generally treat a herpes diagnosis as a non-issue, and many applicants find it doesn’t factor into their application in any meaningful way at all.
I have HPV. Do I need to worry about my life insurance application?
Generally not because of HPV itself. It’s the most common sexually transmitted infection there is, most infections clear on their own within one to two years, and underwriters typically don’t evaluate the virus as a standalone diagnosis. What matters is a downstream finding tied to a persistent strain, such as an abnormal Pap smear, cervical dysplasia, or an HPV-related cancer. If you’ve had one of these findings, that specific history, not the HPV diagnosis, is what’s relevant to discuss.
Can I get life insurance after being treated for chlamydia or gonorrhea?
Yes, and in most cases it’s a non-issue once treatment is completed and documented. Both are bacterial infections that respond reliably to antibiotics. The one complication worth knowing about is pelvic inflammatory disease, which can develop from an untreated infection, but a treated, resolved case of either infection generally has no meaningful bearing on a life insurance application.
Does a syphilis diagnosis affect life insurance differently depending on when it’s treated?
Significantly, yes. Syphilis treated with standard antibiotic therapy during its earlier stages is curable with no lasting health impact, and a documented, completed treatment course from this stage is generally viewed favorably. Left untreated for years or decades, syphilis can progress to a later stage capable of causing serious, sometimes irreversible cardiovascular and neurological damage. A case involving a syphilis diagnosis from many years in the past, especially with unclear treatment history, generally warrants a fuller cardiovascular and neurological workup before underwriting can proceed with confidence.
Has hepatitis C treatment actually improved enough to change how it’s underwritten?
Dramatically, yes. Older interferon-based treatment achieved cure rates as low as under 10% alone, or roughly 30% to 50% combined with ribavirin. Modern direct-acting antiviral treatment achieves sustained virologic response, the clinical definition of cure, in roughly 93% to 98% of cases, typically within a matter of weeks. Applicants who achieve SVR and can document it, along with liver function results, are generally viewed far more favorably than the outdated assumptions many people still carry about this diagnosis.
If I’m cured of hepatitis C, does prior liver damage still matter?
Yes, and this is a genuinely important nuance. Achieving sustained virologic response is the single biggest factor in a strong file, but research following cured patients has found that most of the elevated mortality risk that remains afterward is concentrated in those who already had advanced liver damage, particularly cirrhosis, before the cure was achieved. Two people who both achieved SVR can represent different long-term risk profiles depending on how much liver damage had occurred by the time treatment worked, which is why liver function and fibrosis staging results matter alongside confirmation of the cure itself.
How is hepatitis B different from hepatitis C for underwriting purposes?
Many adults who contract hepatitis B clear it entirely on their own, and a documented, fully resolved acute infection is generally a minor factor. A smaller share of cases become chronic, meaning the virus persists and is managed with antiviral medication aimed at suppressing it to an undetectable or very low level, monitored through regular testing rather than cured outright the way hepatitis C now can be. A well-managed chronic case with years of confirmed viral suppression and stable liver function is viewed very differently than a recently diagnosed case without that history.
What if I’ve already been declined or rated poorly because of an STD history?
A decline from one company is genuinely not the final word. Carriers vary meaningfully in how current their underwriting guidelines are, particularly for hepatitis C, where the shift to modern antiviral treatment has genuinely changed what a well-documented case looks like. Presenting the same file, with the right documentation clearly organized, to a carrier with a more current view of the condition can produce a materially different outcome than the first quote suggested.
About the Author:
Jason Stolz, CLTC, CRPC, DIA, CAA and Chief Underwriter at Diversified Insurance Brokers (NPN 20471358), is a senior insurance and retirement professional with more than 25 years of real-world experience helping individuals, families, and business owners protect their income, assets, and long-term financial stability. As a long-time partner of the nationally licensed independent agency Diversified Insurance Brokers, Jason provides trusted guidance across multiple specialties—including fixed and indexed annuities, long-term care planning, personal and business disability insurance, life insurance solutions, Group Health, Travel Medical and Evacuation Insurance, and short-term health coverage. Diversified Insurance Brokers maintains active contracts with over 100 highly rated insurance carriers, ensuring clients have access to a broad and competitive marketplace.
His practical, education-first approach has earned recognition in publications such as VoyageATL, and contributions from his agency featured in Kiplinger and GoBankingRates— highlighting his commitment to financial clarity and client-focused planning. Drawing on deep product knowledge and years of hands-on field experience, Jason helps clients evaluate carriers, compare strategies, and build retirement and protection plans that are both secure and cost-efficient. Visitors who want to explore current annuity rates and compare options across multiple insurers can also use this annuity quote and comparison tool.
Explore More Life Insurance Options: Browse our complete guide to Life Insurance for Organ, Liver, Kidney & Infectious Disease — covering kidney disease, organ transplants, hepatitis, and HIV/AIDS underwriting from 100+ carriers.
Last Reviewed: September 9, 2026 |
Reviewed by: Jason Stolz, CLTC, CRPC, DIA, CAA
Chief Underwriter, Diversified Insurance Brokers, Inc. | NPN: 20471358 | Diversified Insurance Brokers, Inc. — Licensed in all 50 states
Fact Checked by: Tonia Pettitt, CMIP©
Medicare Specialist, Diversified Insurance Brokers, Inc. | NPN: 14374308 | Diversified Insurance Brokers, Inc. — Licensed in all 50 states
Did you find this content helpful? Leave us a Google review — it helps others find trustworthy guidance too.
Editorial Standards: Diversified Insurance Brokers maintains rigorous editorial standards to ensure accuracy, clarity, and independence in all content. Learn more about our editorial standards and commitment to transparency.
