
Life Insurance for Narcolepsy
As an Independent Life Insurance Broker, we compare rates across 100+ carriers and prescreen every application before submission.
Life Insurance for Narcolepsy

Jason Stolz CLTC, CRPC, DIA, CAA
Narcolepsy is insurable. A diagnosis by itself rarely leads to a decline with fully underwritten life insurance carriers, and published underwriting guidance ranges from Standard rates for stable, well-documented cases to modest table ratings. The factor that moves an offer most is not the label on your records but what your sleepiness has done in the real world: whether symptoms are controlled on treatment, whether cataplexy is frequent or severe, and above all whether you have ever had an accident or near miss while driving. Everything else on this page sits on top of that.
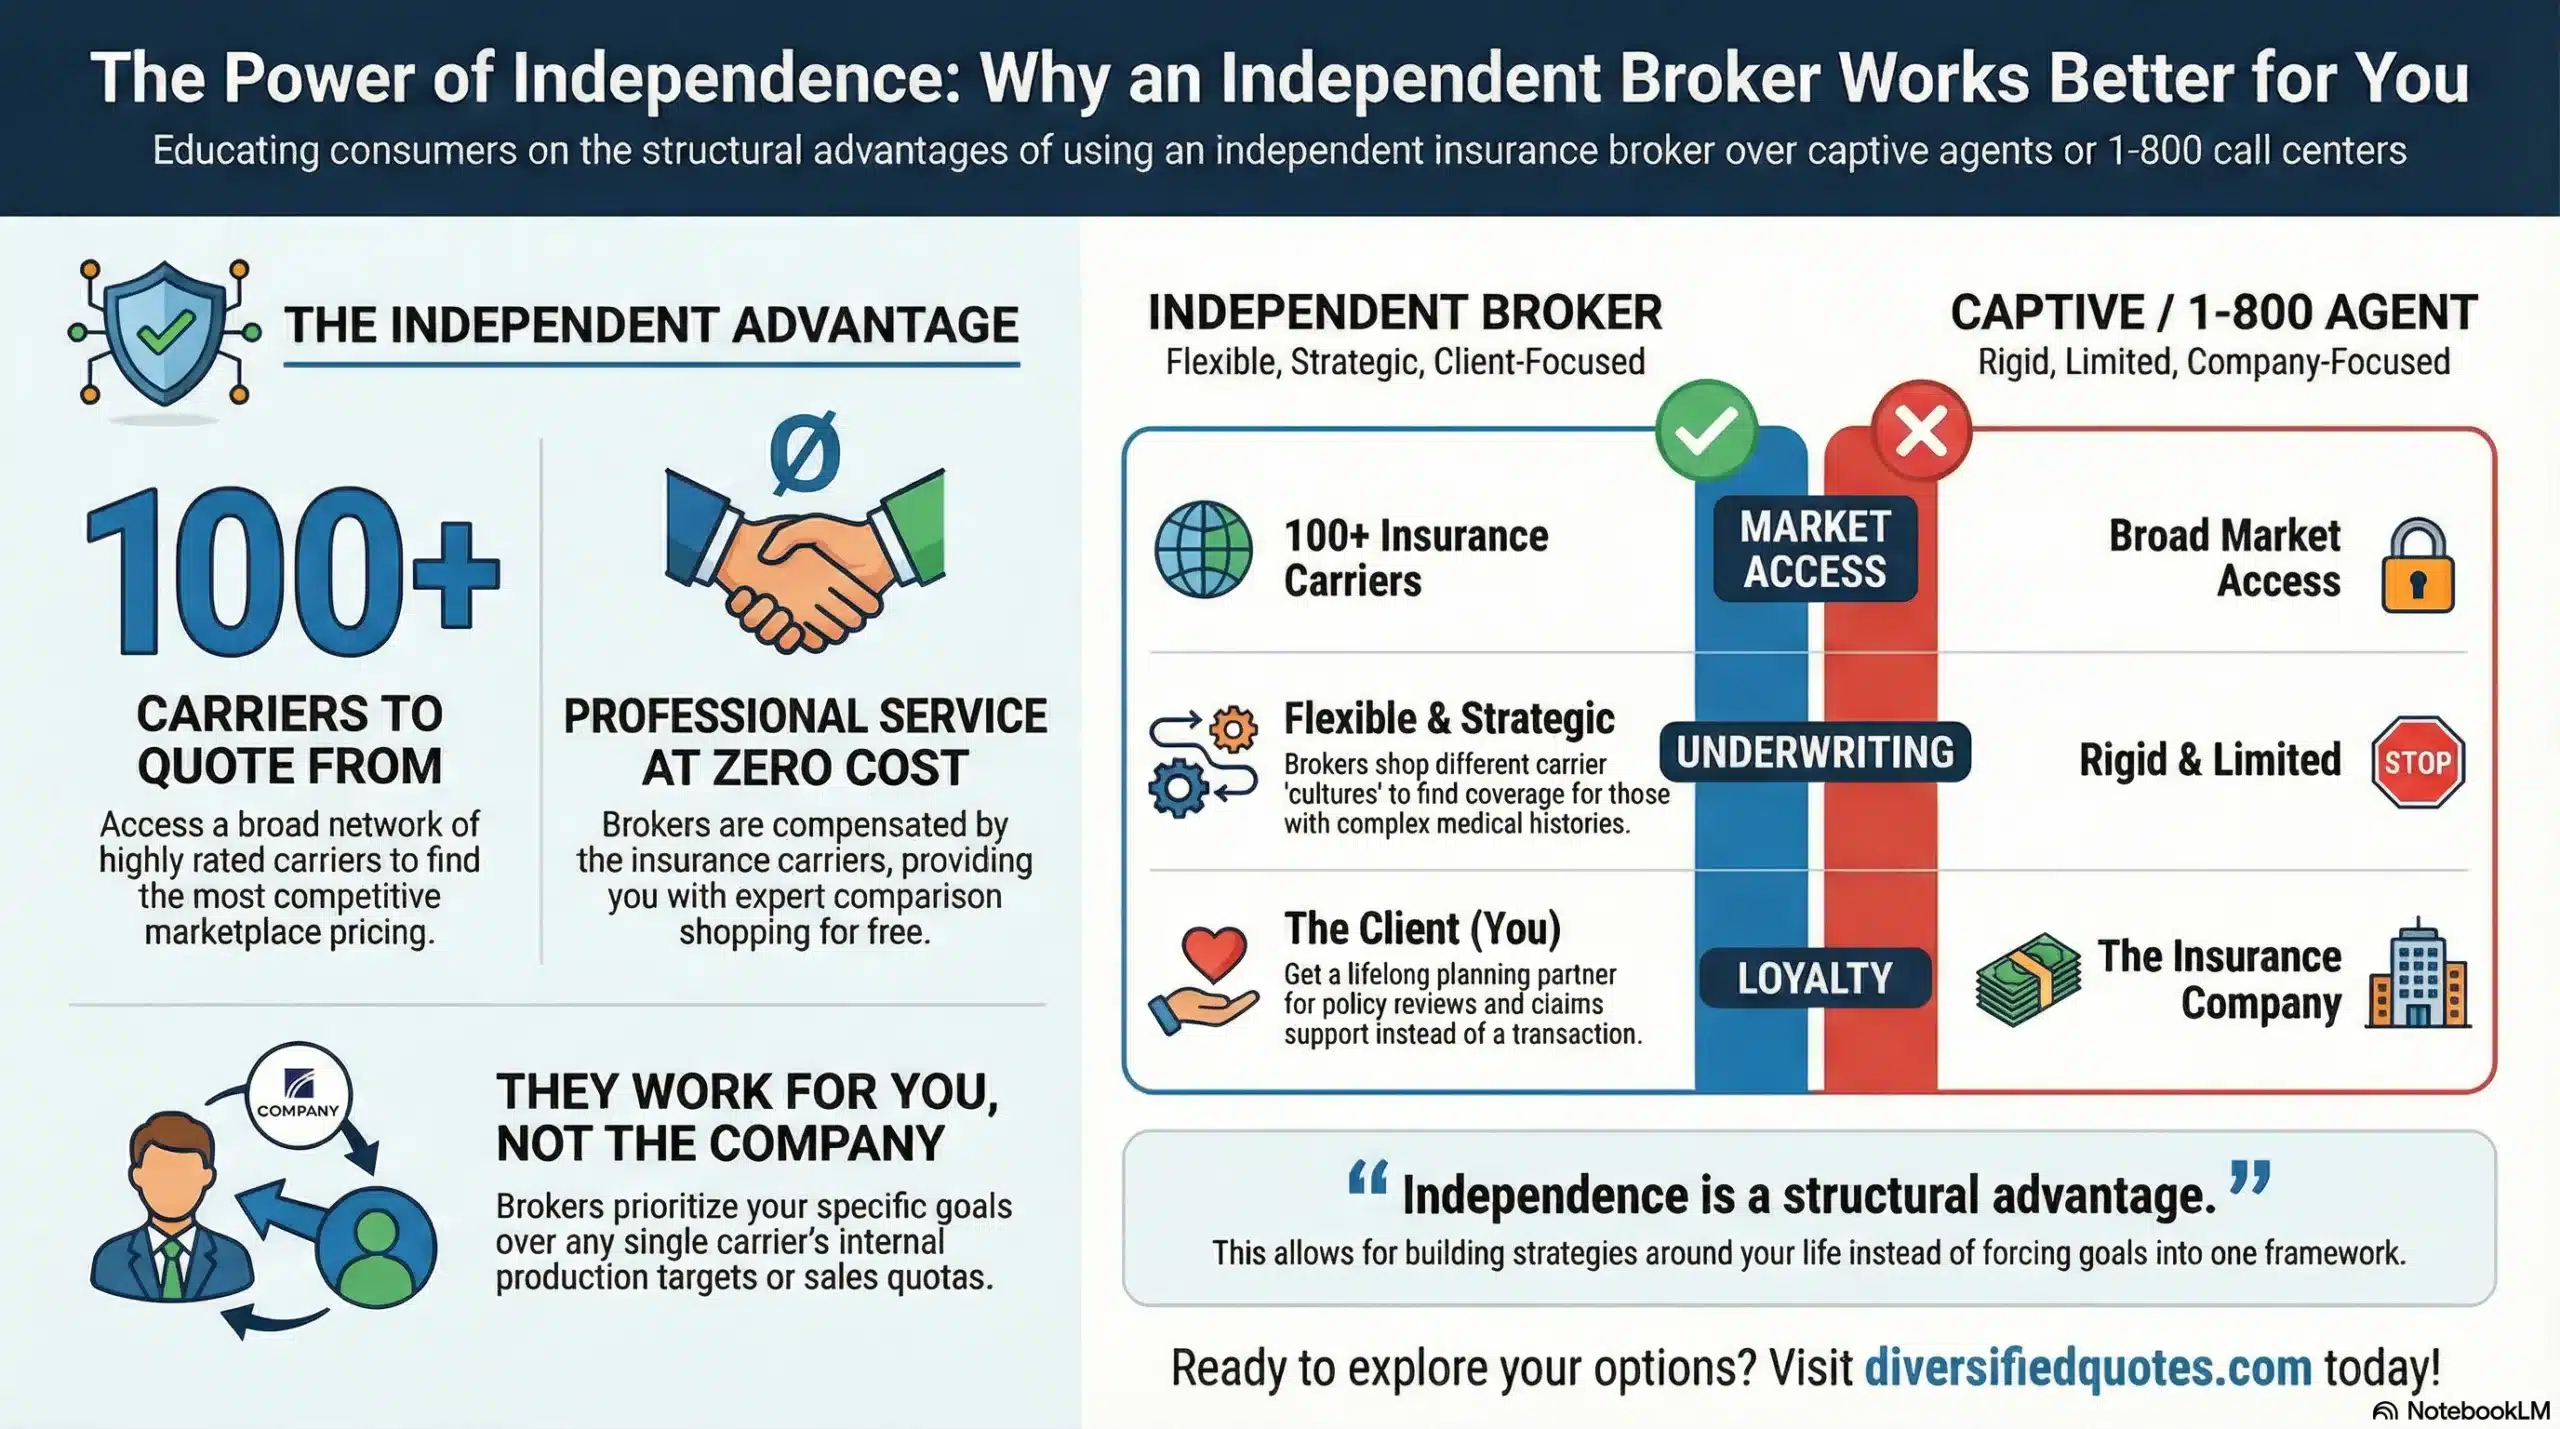
Jason Stolz, CLTC, CRPC, DIA, CAA, is Chief Underwriter at Diversified Insurance Brokers, and narcolepsy is a condition our office places regularly for clients ranging from young adults who were diagnosed in school to established professionals who have managed it for decades. As an independent life insurance broker, our office compares how a range of carriers treat sleep disorders, controlled-substance prescriptions, and driving history, then directs your application to the company most likely to see your case for what it is.
Living with narcolepsy and need life insurance?
See Where I Qualify
What Underwriters Weigh With Narcolepsy
| Factor | What Helps Your Case | What Can Lead to a Rating or Postponement |
|---|---|---|
| Time Since Diagnosis | A confirmed diagnosis with a settled treatment plan | A very recent diagnosis or tests still underway |
| Symptom Control | Daytime sleepiness managed on a stable regimen | Frequent medication changes or poor response to treatment |
| Cataplexy | None, or mild episodes that are well controlled | Frequent attacks or episodes that cause falls |
| Driving Record | A clean record with no sleep-related incidents | Any accident or citation tied to falling asleep |
| Medications | Prescriptions taken as directed under a sleep specialist | Any history of misuse, reviewed under life insurance after substance abuse |
| Occupation | Work that does not depend on constant alertness | Safety-sensitive work; see coverage for high-risk occupations |
| Other Conditions | Sleep apnea treated, blood pressure and heart health normal | Untreated sleep apnea, heart disease, or alcohol misuse |
See Real-Term Rates Side by Side
Life Insurance Quoter
Narcolepsy in Plain Terms
The National Institute of Neurological Disorders and Stroke describes narcolepsy as a chronic neurological disorder that affects the brain’s control of sleep and wakefulness. People with narcolepsy may wake up feeling rested and then feel very sleepy through much of the day, and their nighttime sleep is often broken up by frequent awakenings. Excessive daytime sleepiness is present in everyone with the condition, and it can arrive as a sudden sleep attack that does not improve with more sleep at night.
Other symptoms vary from person to person. Cataplexy is a sudden loss of muscle tone, often triggered by strong emotions such as laughter or fear, ranging from a brief drooping of the eyelids to a full collapse. Sleep paralysis is a short period of being unable to move or speak while falling asleep or waking, sometimes accompanied by vivid hallucinations. Some people also act out their dreams, a condition called REM sleep behavior disorder.
NINDS notes that men and women are affected equally and that symptoms usually begin between ages 7 and 25, although onset can occur at any age. It also notes that narcolepsy is often mistaken for a psychiatric condition, which means the correct diagnosis can take years. That history matters for underwriting, because older records may contain diagnoses or prescriptions that reflect the misdiagnosis rather than the actual condition.
There is no cure, but treatment helps most people manage symptoms well enough to work, drive when alert, raise families, and live full lives. For an underwriter, the question is how well your treatment works and whether your sleepiness has created risk, not simply whether you have the diagnosis.
Type 1, Type 2, and Secondary Narcolepsy
Narcolepsy is divided into types, and knowing which one appears in your records helps explain how an underwriter will read your file. According to NINDS, type 1 narcolepsy, formerly called narcolepsy with cataplexy, is diagnosed by low levels of the brain chemical hypocretin, also called orexin, or by the combination of cataplexy and excessive sleepiness on a specialized nap test. The loss of the brain cells that produce hypocretin is the main cause of type 1, and researchers believe an autoimmune process destroys them in people with a genetic predisposition.
Type 2 narcolepsy, formerly called narcolepsy without cataplexy, involves excessive daytime sleepiness, usually without cataplexy, and hypocretin levels are normal. NINDS describes its symptoms as typically less severe than those of type 1. From an underwriting standpoint, type 2 often reads as the simpler case, since the absence of cataplexy removes one source of potential falls and injuries.
Secondary narcolepsy is different. It results from an injury to the hypothalamus, the area of the brain that regulates sleep, and NINDS notes that it may come with other neurological problems. Brain injuries, tumors, and other diseases affecting the regions that control wakefulness can cause it. When narcolepsy is secondary, the underwriter’s attention shifts to the underlying cause, and a tumor or significant brain injury will be evaluated on its own terms.
If you are not sure which type you have, your sleep specialist’s notes will say. Having that answer before you apply allows the underwriter to classify the case correctly from the start instead of requesting records to find out.
How Carriers Rate Narcolepsy
Carriers do not publish a single standard for narcolepsy, and the guidance that is available varies. One major U.S. carrier’s field underwriting guide places narcolepsy in its Table A to C range, a modest rating above Standard. Other underwriting guidance treats narcolepsy that has been fully investigated and is stable at Standard rates, but only after at least six months have passed since diagnosis. Between those two reference points sits most of the market, and where a particular applicant lands depends on the details of the case.
Table ratings add a percentage to the Standard premium, and each step up the table increases the cost. Our guide to how table ratings affect premiums explains how those steps work. For an applicant with well-controlled type 2 narcolepsy, no cataplexy, a clean driving record, and no other health issues, the most favorable carriers may offer Standard or close to it. For an applicant with frequent cataplexy, a recent medication change, or a sleep-related accident, a table rating or a postponement becomes more likely.
Preferred classes are harder to reach with narcolepsy than with many other chronic conditions, because the condition is ongoing, treatment often involves controlled substances, and the risk of an accident is part of the underwriting picture. That does not mean Preferred is impossible at every carrier, but applicants should approach the process expecting Standard as a realistic target for a well-controlled case.
The practical takeaway is that carrier selection matters a great deal. The same file can draw a Standard offer from one company and a table rating from another, which is why our office prescreens the case before any formal application goes out.
Your Driving Record Carries Extra Weight
For most life insurance applicants, the motor vehicle report is a formality checked for speeding tickets and serious violations. For an applicant with narcolepsy, it becomes one of the most important documents in the file. Carriers routinely pull driving records, and an underwriter reviewing a narcolepsy case will look closely for accidents, especially single-vehicle accidents, and for any notes suggesting that sleepiness played a role.
The reason is simple. Much of the underwriting concern with narcolepsy centers on the risk of accidents, and falling asleep at the wheel is the most serious version of that risk. NINDS advises people with narcolepsy to avoid driving when sleepy. An applicant who follows that advice, who has a clean record, and whose doctor documents good control is presenting exactly the profile underwriters want to see.
A past accident does not automatically rule out coverage, but the circumstances matter. An accident that occurred before diagnosis and led to the diagnosis and treatment tells a very different story from one that occurred recently while on treatment. A clear explanation, ideally supported by your sleep specialist’s notes showing improvement since the event, can make a meaningful difference in how the incident is weighed.
If your license was ever suspended or restricted for medical reasons, or if your doctor has advised you not to drive, disclose it. The application questions about driving are specific, and accurate answers protect the policy. Our office reviews your driving history with you before you apply so that the explanation is ready when the underwriter asks.
Commercial Drivers and Safety-Sensitive Jobs
Occupation is the second place where narcolepsy can affect underwriting. Federal rules for interstate commercial drivers bar anyone with a condition likely to cause a loss of consciousness or loss of the ability to control the vehicle, and the Federal Motor Carrier Safety Administration has applied that standard to narcolepsy. Its Medical Review Board recommended that people with narcolepsy be ineligible for a commercial driver’s license even with treatment, although individual exemption requests can be filed.
That means most people diagnosed with narcolepsy are not driving trucks across state lines. Our page on life insurance for truck drivers covers how carriers evaluate commercial driving in general, and a driver who receives a narcolepsy diagnosis while holding a CDL should expect questions about current duties and whether the license is still active.
Other jobs raise similar questions. Work at heights, operation of heavy machinery, piloting, and other roles where a sudden sleep attack or cataplexy episode could cause serious harm may lead an underwriter to ask about job duties and any accommodations in place. NINDS notes that the Americans with Disabilities Act allows adults with narcolepsy to request workplace adjustments, such as scheduled naps or arranging demanding tasks for the times they are most alert.
A clear description of what you do each day helps. An engineer who designs equipment faces different questions than one who operates it, even if both carry the same job title. When the application describes your actual duties accurately, the underwriter can price the real risk rather than the worst case for the title.
Wake-Promoting Medications and Stimulants on Your Record
Prescription history is the first place most underwriters see narcolepsy, and the medications involved can look concerning to someone reading them without context. NINDS lists wake-promoting agents such as modafinil, armodafinil, and solriamfetol as typical first-line treatments for daytime sleepiness, and amphetamine-like stimulants such as methylphenidate when those agents are not effective. Several of these drugs are controlled substances, and stimulants in particular are tracked closely.
The same stimulants are widely prescribed for attention disorders, so a prescription check alone does not tell an underwriter which condition is being treated. Applicants who also have an attention disorder will find that our page on life insurance with ADHD covers how those prescriptions are evaluated. For narcolepsy, the application should state the diagnosis and the prescribing sleep specialist so the underwriter connects the medication to the right condition.
What underwriters look for is a stable, supervised pattern. A consistent prescription from one prescriber, filled at regular intervals and at the prescribed dose, reads as responsible treatment. Multiple prescribers, early refills, or doses that climb without explanation can raise questions about misuse, which carriers evaluate separately and seriously.
NINDS calls for careful monitoring for serious side effects when stimulants are used, and stimulants commonly raise heart rate and blood pressure. Regular checkups that document normal blood pressure while on treatment help the underwriter see that the medication is being managed safely, and they support a better class at the same time.
Sodium Oxybate, Alcohol, and Underwriting
Sodium oxybate is one of the most effective treatments for narcolepsy and one of the most closely watched. NINDS notes that it is approved for both cataplexy and daytime sleepiness and that its distribution is tightly restricted. It is taken at night, it is a central nervous system depressant, and its labeling warns against combining it with alcohol or other sedating medications. A lower-sodium mixed-salt version is also available, which matters for patients who need to limit sodium for blood pressure or heart reasons.
For an underwriter, an oxybate prescription is not a red flag on its own. It signals that a sleep specialist is managing the case and that the patient is enrolled in a supervised distribution program. What the underwriter will focus on is alcohol. Because combining oxybate with alcohol is dangerous, any history of heavy drinking, alcohol-related driving offenses, or alcohol treatment draws more attention than it would for another applicant.
Applicants on oxybate should answer the alcohol questions on the application carefully and accurately. Someone who does not drink, or who drinks only rarely and not on treatment nights, is presenting a responsible picture. If your specialist’s notes mention counseling about alcohol, that is helpful context rather than a concern, since it shows the risk was discussed and managed.
The lower-sodium version can also help in a less obvious way. If you switched formulations because of blood pressure, the switch shows that the issue was identified and addressed. Our office makes sure that context reaches the underwriter, so a formulation change reads as careful management rather than as a new problem.
Antidepressants for Cataplexy Are Not a Depression Diagnosis
One of the most common sources of confusion in narcolepsy files is the antidepressant. NINDS lists tricyclic antidepressants such as imipramine and clomipramine, along with certain reuptake inhibitors such as venlafaxine and fluoxetine, as treatments for cataplexy. In these cases the medication is used for its effect on REM sleep and muscle tone, not to treat mood.
A prescription check, however, shows only the drug name. An underwriter who sees venlafaxine or fluoxetine without context may assume a diagnosis of depression or anxiety and ask about psychiatric history, hospitalizations, and treatment, which slows the case and can affect the offer. Our page on life insurance with depression explains how carriers evaluate mood disorders, and it is worth understanding that review so you can head it off when it does not apply.
The fix is simple. On the application, list the antidepressant and state that it is prescribed for cataplexy by your sleep specialist. If the prescriber is a neurologist or sleep physician rather than a psychiatrist, that detail reinforces the point. When the records match the explanation, the underwriter can move on.
There is a second layer to this. Because narcolepsy is often mistaken for a psychiatric condition before it is correctly diagnosed, some applicants have older records showing depression or another psychiatric label that was later revised. If that applies to you, a short note from your current specialist explaining the history can prevent an outdated diagnosis from following you into the underwriting decision.
Newer Treatments and How Underwriters See Them
Treatment options for narcolepsy have expanded, and underwriters are still catching up with some of them. NINDS describes pitolisant as a non-scheduled medication that works on histamine receptors in the brain, approved for adults with narcolepsy and for children six and older with daytime sleepiness. Because it is not a controlled substance, it may draw less attention in a prescription check than stimulants or oxybate.
NINDS also notes the approval of oveporexton for adults with type 1 narcolepsy, a medication designed to address the underlying loss of hypocretin signaling rather than only the symptoms. For patients with type 1, that represents a meaningful change in how the condition is treated. For underwriting, it is new enough that some carriers may not yet have specific guidance on it, which makes clear documentation from your specialist especially valuable.
New medications can help an application in two ways. If a newer treatment has brought better control, the records will show fewer symptoms, fewer cataplexy episodes, and a more stable daily routine, which is exactly what the underwriter is looking for. If you switched away from a controlled substance, the prescription history becomes simpler to read.
The timing of a switch matters, though. An application submitted in the middle of a medication change can look unsettled even when the change is going well. Waiting until your specialist has confirmed that the new regimen is working, usually documented at a follow-up visit, gives the underwriter a stable picture rather than a transition. Our office can help you judge when the record is ready.
Cataplexy Is Not a Seizure
Cataplexy can look alarming to someone who has never seen it. A person’s knees may buckle, the head may drop, or in severe cases the body may collapse completely. To an underwriter reading a description of a collapse, the first comparison that comes to mind may be a seizure, and seizure disorders are underwritten with close attention to frequency, control, and loss of consciousness.
NINDS makes an important distinction: even during the most severe cataplexy episodes, people remain fully conscious. It also notes that the episodes are not dangerous if the person is in a safe place. That difference matters, and your records should reflect it. If earlier notes described episodes as possible seizures before narcolepsy was diagnosed, a clear statement from your current specialist confirming cataplexy and ruling out seizure activity helps prevent the case from being evaluated under the wrong standard. Our page on life insurance with epilepsy and seizures shows how differently those conditions are reviewed.
Cataplexy still matters to underwriting. Frequent episodes, episodes that lead to falls and injuries, or episodes that are poorly controlled can support a higher rating, particularly when combined with driving or occupational exposure. Mild or well-controlled cataplexy, on the other hand, often adds little to the assessment beyond the narcolepsy itself.
When describing cataplexy on an application or in a conversation with our office, be specific: how often it happens, what triggers it, whether it ever causes a full collapse, and whether treatment has reduced it.
Worried that cataplexy or your medications will hurt your rate?
Review My Situation
Sleep Apnea and Other Conditions That Travel With Narcolepsy
Narcolepsy rarely appears alone in an underwriting file. NINDS notes that sleep apnea, insomnia, and periodic leg movements can disrupt nighttime sleep in people with narcolepsy and make daytime sleepiness worse. REM sleep behavior disorder, in which a person acts out dreams, can also occur and in some cases signals another neurological disorder.
Sleep apnea is the one underwriters focus on most, because untreated apnea is associated with heart and blood pressure problems and adds to the risk of drowsy driving. Our page on life insurance with sleep apnea explains how severity and treatment affect pricing. An applicant with both narcolepsy and sleep apnea will be assessed on both, and good treatment of the apnea can keep it from compounding the narcolepsy rating.
Treatment compliance is the key. Many CPAP machines record usage, and a compliance report showing consistent nightly use is strong evidence. Our guide for applicants who use CPAP therapy covers what carriers typically ask for. If your sleep study for narcolepsy also evaluated breathing, the report will show whether apnea was present and how severe it was.
Insomnia and restless legs are generally minor factors on their own, but they belong on the application when they are diagnosed and treated. REM sleep behavior disorder may prompt questions about whether any other neurological condition has been considered, so a specialist’s note addressing that question helps close it.
Heart Health and Narcolepsy
NINDS notes that people with narcolepsy face a higher risk of heart disease and other serious heart problems, and it recommends that heart health be monitored regularly and considered when choosing treatments. That finding gives underwriters a reason to look closely at blood pressure, cholesterol, and any cardiac history in a narcolepsy file.
Several narcolepsy treatments interact with heart health. Stimulants commonly raise heart rate and blood pressure, and the original form of sodium oxybate carries a significant amount of sodium. Carriers set their own blood pressure limits for each rate class, as our page on life insurance with high blood pressure describes.
The good news is that heart health is measurable and often controllable. Regular checkups that show normal or well-controlled blood pressure, healthy cholesterol, and no cardiac symptoms help offset the general risk associated with narcolepsy. If you do have a heart condition, it will be rated on its own, and our guide to life insurance with heart disease explains how carriers approach it.
From a planning standpoint, this is one more reason to apply when your health is well documented and stable. The paramedical exam that accompanies many applications includes blood pressure readings and blood work, and favorable results recorded at the time of application become part of the evidence the underwriter relies on.
When Narcolepsy Starts Young
Because symptoms usually begin between ages 7 and 25, many people with narcolepsy are diagnosed as children, teenagers, or young adults. That timing creates two common situations: parents who want coverage for a child who has been diagnosed, and young adults buying their first policy with a diagnosis already in their records.
For parents, a policy on a child is usually about locking in future insurability rather than replacing income. Our page on life insurance for kids explains the options. A child with narcolepsy will be underwritten, and the outcome depends on the same factors that apply to adults, including symptom control and the type of narcolepsy. NINDS notes that children and teens can work with their schools on schedules, daytime medication, and other accommodations, and records of that kind of structured management are helpful.
Young adults face a different decision. Buying coverage early, while the condition is stable and before other health issues appear, can secure a class that stays with the policy for its full term. Our guide to no-exam life insurance for young adults covers the fastest routes, although a narcolepsy diagnosis with controlled-substance prescriptions often moves an application into traditional underwriting.
Term coverage with a conversion option is often a smart fit at a young age. It keeps the premium low while protecting the right to switch to permanent coverage later without new medical questions, which can matter for someone with a lifelong condition.
Workplace Coverage Versus a Policy You Own
Many people with narcolepsy already have some life insurance through work, and it is worth understanding what that coverage does and does not do. Employer group life plans often provide a basic benefit, frequently a multiple of salary, without any health questions, and many allow employees to buy additional amounts up to a guaranteed limit when they first become eligible. For someone with a chronic condition, that guaranteed amount is valuable because it bypasses individual underwriting entirely.
The weakness of group coverage is that it belongs to the job. If you change employers, are laid off, reduce your hours below the plan’s eligibility threshold, or retire, the coverage usually ends. Most plans offer a way to convert or continue the coverage when you leave, but converted policies are often expensive, and the amount available may be limited. A person whose health makes individual coverage harder to buy is exactly the person who is most exposed when workplace coverage disappears.
Narcolepsy can make that risk more pressing. Some people with the condition change roles or employers over time to find work that fits their symptoms, and each move can put group coverage in question. An individually owned policy remains yours as long as you keep paying the premium, no matter which employer you work for or how many hours you put in.
The most resilient approach for many families is to treat workplace coverage as a supplement rather than the foundation. An individually owned term or permanent policy, purchased while your condition is stable and well documented, provides the core protection, and the group benefit adds to it for as long as you hold the job. If you are still within an enrollment window at work, take the guaranteed amount, and then use individual underwriting to build the rest of the plan. Our office can review your employer benefits alongside individual options so the two work together.
If a Carrier Declines
Most applicants with narcolepsy can find fully underwritten coverage, but some cases are harder: a recent sleep-related accident, severe and uncontrolled cataplexy, a history of medication misuse, or narcolepsy secondary to a serious brain condition. A decline from one carrier is not the end of the road, because underwriting standards differ from one company to the next, and a postponement may simply mean waiting until the record is more settled.
For applicants who need coverage now and cannot qualify through medical underwriting, a guaranteed issue term program built around employment rather than health is worth considering. Full program details appear on our page about guaranteed issue term life insurance. It is available to people actively working at least 20 hours a week, asks no health questions, and offers term coverage up to $150,000 with age-based maximums, in 10-year or 20-year terms, for issue ages up to 70.
The program is issued by Assurity Life Insurance Company and offered through Live Well USA, a membership association. Membership is required to enroll and to keep coverage in force, and it carries a monthly fee in addition to the premium. Budget for that fee alongside the premium when comparing options. The program is not available in Washington.
Guaranteed issue coverage costs more per dollar of coverage than a fully underwritten policy for a healthy applicant, so it works best as a fallback or as a bridge while a medically underwritten policy is pursued. Our office can lay out both paths side by side.
Records That Help Your Case
Narcolepsy cases move fastest when the underwriter can see the diagnosis, the treatment, and the results without chasing records. NINDS explains that diagnosis typically involves a clinical exam, a detailed history, and often a sleep journal, followed by two tests: an overnight sleep study called a polysomnogram and a multiple sleep latency test, which measures how quickly a person falls asleep and enters REM sleep during daytime naps. Some people also have a spinal fluid test that measures hypocretin.
Before you apply, gather the dates and results of those tests if you have them, the name and contact information of your sleep specialist, and a current list of medications with doses. Note when each medication was started and, if any were stopped, why. If your specialist uses a symptom scale such as the Epworth Sleepiness Scale, recent scores that show improvement are useful evidence of control.
Add the history the underwriter will ask about anyway: how often cataplexy occurs and whether it has caused falls, any driving incidents and their circumstances, any work restrictions or accommodations, and any other sleep conditions such as apnea, with CPAP compliance data if you use one. If your narcolepsy is secondary, have the records for the underlying condition ready.
Carriers also check industry databases. The Medical Information Bureau holds coded information from prior applications, and our explanation of what MIB means for applicants covers how that works. An application that matches what those databases and your medical records show is approved faster and is far less likely to be questioned later. Our office organizes this information before anything is submitted, so the underwriter receives a complete file rather than a series of follow-up requests.
Common Mistakes Applicants With Narcolepsy Make
The most serious mistake is leaving narcolepsy off the application. The prescription check will show the medications, and a stimulant or oxybate prescription without a disclosed diagnosis invites far harder questions than the diagnosis would have. A policy issued on incomplete answers can be contested within the contestable window, usually the first two years a policy is in force, and a contested claim can leave a family without the protection they were counting on.
The second mistake is applying too soon. A diagnosis that is only weeks old, tests that are still being completed, or a medication regimen that is still being adjusted can lead to a postponement, and a postponement is something later applications typically ask you to disclose. Waiting until treatment has settled usually produces a better result.
The third mistake is letting medications speak for themselves. Antidepressants used for cataplexy, stimulants used for sleepiness, and oxybate taken at night all need context. Without it, the underwriter may assume a psychiatric condition, an attention disorder, or a substance concern that does not exist.
The fourth mistake is understating driving history. An accident that is explained clearly, with the circumstances and what changed afterward, is something an underwriter can work with. An accident that appears on the motor vehicle report after being left off the application damages credibility across the whole file.
The last mistake is applying to carriers at random. Carriers differ meaningfully in how they view sleep disorders and controlled-substance prescriptions, and a decline from the wrong company can complicate later applications. A short prescreen avoids that.
Want your case prescreened before a formal application?
Start My Prescreen
Disability Insurance With Narcolepsy
Life insurance and disability insurance treat narcolepsy very differently. A life insurer asks whether the condition affects mortality, and for a well-controlled case the answer can be Standard or close to it. A disability insurer asks whether the condition could keep you from working, and narcolepsy, with its daytime sleep attacks and potential effect on job duties, raises that question directly.
The published guidelines reflect that difference. At least one major carrier’s individual disability underwriting guide lists narcolepsy as a decline, and other underwriting guidance has long indicated that disability coverage is not normally offered for the condition. That makes individually underwritten disability coverage difficult to obtain once narcolepsy has been diagnosed.
Group coverage through an employer is often the most practical route. Many employer plans provide disability coverage without individual medical underwriting, especially for amounts offered at initial enrollment, and our page on guaranteed issue group disability insurance explains how that works. Group plans may include limits on pre-existing conditions during the early period of coverage, so the plan documents should be reviewed carefully.
For working adults with narcolepsy, the combination of employer disability coverage, workplace accommodations under the Americans with Disabilities Act, and an individually owned life insurance policy often provides the most complete protection available. Our office handles both life and disability insurance and can review what you have and where the gaps are.
How Our Office Helps
Every narcolepsy case starts with a conversation about your history. Jason and our office ask about your type of narcolepsy, when you were diagnosed, your current medications, how often cataplexy occurs, your driving record, your occupation, and any related conditions such as sleep apnea. That review shows quickly which parts of your history are strengths and which need to be explained.
From there, we prescreen the case with carriers whose guidelines fit your profile, without submitting a formal application. That step identifies which companies are likely to offer Standard or close to it, which would rate the case more heavily, and whether waiting for a medication change to settle would improve the result. Only then do we recommend where and when to apply.
After the application goes in, we supply the explanations the underwriter will need, including the purpose of each medication and the circumstances of any driving incident, and we follow up on records requests from your sleep specialist. When an offer comes back, we explain it before you accept it and compare it with other carriers’ views if it is higher than expected. If medical underwriting is not possible right now, we lay out the guaranteed issue option and a plan for revisiting fully underwritten coverage later. Because we are independent, the recommendation follows your profile rather than a single company’s rules.
Ready to find the right carrier for your narcolepsy case?
Talk to Our Office
Financial Protection Essentials
Practical guides for protecting your family and income while living with a chronic condition.
Talk With an Advisor Today
Choose how you’d like to connect—call or message us, then book a time that works for you.
Schedule here:
calendly.com/jason-dibcompanies/diversified-quotes
Licensed in all 50 states • Fiduciary, family-owned since 1980
Frequently Asked Questions
Can I get life insurance if I have narcolepsy?
Yes. Most applicants with narcolepsy can qualify for fully underwritten coverage, with outcomes ranging from Standard rates for stable, well-documented cases to modest table ratings when cataplexy, recent medication changes, or driving incidents are involved. Carrier choice makes a large difference. Our overview of life insurance with health issues explains how carriers weigh chronic conditions.
Will cataplexy get me declined?
Usually not. Mild or well-controlled cataplexy often adds little to the assessment, while frequent episodes that cause falls can lead to a higher rating, especially combined with driving or hazardous work. A clear specialist note describing frequency and control helps. If a carrier has already declined you, our guide on coverage after a prior decline explains what to do next.
Does taking sodium oxybate hurt my application?
Not by itself. It shows that a sleep specialist is managing your care. Because oxybate should not be combined with alcohol, underwriters pay closer attention to drinking history, so careful, accurate answers to the alcohol questions matter. Our page on life insurance and alcohol use explains how drinking history is reviewed.
Can I add coverage for my child who has narcolepsy?
Often, yes. A child can be insured on a separate policy or, in many cases, under a child rider attached to a parent’s policy, and the diagnosis may be reviewed depending on the product. A rider can also preserve the child’s right to convert to an individual policy later. Our page on life insurance with a child rider explains how these riders work.
Can I skip the medical exam with narcolepsy?
Sometimes. Accelerated programs rely on prescription and database checks, and controlled-substance prescriptions often move a narcolepsy case into traditional underwriting. Applicants with type 2 narcolepsy on non-scheduled treatment and a clean history have a better chance. The screening steps are described in our guide to instant decision life insurance options.
Should I buy term coverage now and convert it later?
For many people with narcolepsy, that is a sound plan. Term coverage keeps premiums low during the years when obligations are highest, and a conversion option lets you switch to permanent coverage later without new medical questions, protecting you if your health changes. Our page on converting term to permanent coverage explains how conversion works.
I received a table rating. Is it worth shopping the case again?
Often it is. Carriers differ in how they view sleep disorders, stimulant prescriptions, and driving history, and a rating from one company may not hold at another. Better documentation from your sleep specialist can also change the outcome. Our office can review the offer through a second opinion on your quote.
How much coverage should I buy with narcolepsy?
The amount should reflect your income, debts, mortgage, children, and what a surviving spouse would need, not the diagnosis. If narcolepsy affects your earning years or career path, factor that into how long coverage should last. Our guide to figuring out your coverage amount walks through the calculation step by step.
I was just diagnosed. Should I apply now or wait?
If you can wait, it usually pays to. Some underwriting guidance calls for at least six months after diagnosis, with testing complete and treatment settled, before offering Standard terms. An application submitted during that early period may be postponed, and many applications later ask whether coverage was ever postponed. If you need coverage immediately, our office can identify carriers or guaranteed issue options that fit the situation.
About the Author:
Jason Stolz, CLTC, CRPC, DIA, CAA and Chief Underwriter at Diversified Insurance Brokers (NPN 20471358), is a senior insurance and retirement professional with more than 25 years of real-world experience helping individuals, families, and business owners protect their income, assets, and long-term financial stability. As a long-time partner of the nationally licensed independent agency Diversified Insurance Brokers, Jason provides trusted guidance across multiple specialties—including fixed and indexed annuities, long-term care planning, personal and business disability insurance, life insurance solutions, Group Health, Travel Medical and Evacuation Insurance, and short-term health coverage. Diversified Insurance Brokers maintains active contracts with over 100 highly rated insurance carriers, ensuring clients have access to a broad and competitive marketplace.
His practical, education-first approach has earned recognition in publications such as VoyageATL, and contributions from his agency featured in Kiplinger and GoBankingRates— highlighting his commitment to financial clarity and client-focused planning. Drawing on deep product knowledge and years of hands-on field experience, Jason helps clients evaluate carriers, compare strategies, and build retirement and protection plans that are both secure and cost-efficient. Visitors who want to explore current annuity rates and compare options across multiple insurers can also use this annuity quote and comparison tool.
Explore More Life Insurance Options: Browse our complete guide to Life Insurance for Chronic, Autoimmune & Neurological Conditions — covering arthritis, lupus, MS, Crohn's, epilepsy, and Parkinson's from 100+ carriers.
Last Reviewed: October 9, 2026 |
Reviewed by: Jason Stolz, CLTC, CRPC, DIA, CAA
Chief Underwriter, Diversified Insurance Brokers, Inc. | NPN: 20471358 | Diversified Insurance Brokers, Inc. — Licensed in all 50 states
Fact Checked by: Tonia Pettitt, CMIP©
Medicare Specialist, Diversified Insurance Brokers, Inc. | NPN: 14374308 | Diversified Insurance Brokers, Inc. — Licensed in all 50 states
Did you find this content helpful? Leave us a Google review — it helps others find trustworthy guidance too.
Editorial Standards: Diversified Insurance Brokers maintains rigorous editorial standards to ensure accuracy, clarity, and independence in all content. Learn more about our editorial standards and commitment to transparency.
